Helpline

0300 111 1234

Employment advice

Employment: PKD and work

This information is for people with polycystic kidney disease (PKD) who are employed or looking for a job in England, Wales or Scotland. Employment law differs in Northern Ireland — please see links near the end of this page for information.

Having PKD might affect your ability to work. For example, you might need time off or need to change your work pattern. On this page we outline the laws on disability and equality that your employer must follow. We also give tips on how to approach issues with your employer.

We understand that if PKD is affecting your ability to work, this can be very stressful. We hope this information helps you. Please also seek personal advice from organizations such as Citizens Advice and the Equality Advisory & Support Service. Their contact details are near the end of this page.

Disclaimer

This webpage aims to give you general tips on employment and PKD but is not a comprehensive overview of equality and employment law. Because of differences in laws, some of the content is not accurate for people living in Northern Ireland. Please seek expert advice for your individual situation.

Contents

Key Facts

  • If PKD is affecting your normal daily life, you might be classed as disabled.
  • This gives you certain rights. Your employer must make ‘reasonable adjustments’ to help you do your job.
  • Adjustments could include changing your working hours or letting you work from home, for example.
  • Your employer will need to understand how PKD affects you so they can think about reasonable adjustments.
  • If you don’t think you’re classed as disabled, it’s worth checking the rules on this. They may be broader than you think.
  • If you’re not disabled, you can still chat to your employer about adjusting your work. However, there’s not a law they need to follow.
  • You’re likely to be able to claim sick pay if you’re off sick.
  • If you have more time off than your employer’s absence and sickness policy allows, you may need to go to meetings about this.
  • Uncommonly, employers may dismiss an employee if they feel the employee can’t do their job. Employers must first consider all other options (including reasonable adjustments) and show that the business is being significantly impacted before they dismiss a person with a disability.
  • If you’re looking for a new job, potential employers can only ask certain questions about health and disability.
  • If you think your employer is treating you unfairly, you could raise a grievance or make a claim with an employment tribunal.

A photo of three people talking happily at a desk with laptops

Is PKD affecting your day-to-day work?

If PKD is impacting your day-to-day life, you might be classed as disabled. PKD is progressive, meaning it gets worse over the years. It might affect you more, or in different ways, as you get older.

You may need to take planned time off work for medical appointments and procedures. You might also need to take unplanned leave (sick leave) if PKD makes you unwell.

Examples of disability caused by PKD are:

  • Your kidneys don’t work well and this makes you very tired. This affects your daily activities. For example, you can’t concentrate in long meetings and so need important things written in email.
  • Your PKD is causing anxiety, which is affecting your daily activities. You need more time to answer questions or solve problems. You struggle to think clearly under pressure.
  • Your kidneys are causing pain. This means you can’t do some manual tasks or sit in one position for a long time. 
  • Your medicines make you need the toilet often.

How is your right to work protected if you’re disabled?

The Equality Act 2010 is British legislation (law) that protects people from discrimination.

Disability means ‘a physical or mental impairment that has a substantial and long-term negative effect on your ability to do normal daily activities’.

  • Substantial means more than minor or trivial.
  • Long-term means 12 or more months.

Some people with PKD are classed as having a disability.

If you’re discriminated against because of your disability this means someone treats you less favourably than they would treat others because you have a disability.

Under the Equality Act 2010, employers must make ‘reasonable adjustments’ to make sure workers with disabilities are not at a substantial disadvantage when doing their jobs. Examples of reasonable adjustments are altering your work area or letting you come back to work gradually after illness. We give more examples later.

The rules on discrimination at work apply to people on zero-hours contracts. They also apply to self-employed persons (freelancers, consultants and contractors) who are contracted by another company.

The Equality Act 2010 does not apply in Northern Ireland. Contact the Quality Commission for Northern Ireland for information on disability laws in Northern Ireland.

A photo of a labourer laying cement on a building site

Working with your employer to enable you to do your job if you’re disabled

Many employers know what they must do for the Equality Act and are caring and supportive. Others might be less aware of what they should do or might sometimes fail to support employees as needed.

If you feel that your employer doesn’t understand or meet your needs, here are some tips:

1. Explain your PKD

Your employer can only support you and think about reasonable adjustments if they understand how PKD affects you. Help them understand. For example, if you have a ‘return to work’ meeting after time off due to PKD, mention that you have PKD and explain what it is.

You could give your employer permission to request a report from your GP about your health and PKD symptoms.

You could also have an occupational health assessment. In this, an occupational health adviser will ask about your health and needs. They’ll make a report for your employer about what would help you.

Let your employer know if you’re happy to do either of these things.

Or, you could ask your manager for a meeting to discuss your health. Explain how PKD affects you at the meeting.

2. Get medical reports

Medical reports from your GP and occupational health can show how PKD affects your work. These reports should give details about your PKD and how it is impacting (or could impact) your work.

Your doctor and occupational health can suggest reasonable adjustments for your employer to think over. They can also confirm whether you’re classed as disabled.

You have the right to see these reports before they go to your employer.

When your employer gets the report, they should arrange a meeting with you to discuss it. If they don’t, ask for one.

3. Ask for reasonable adjustments to be made

Once your employer is aware of your disability, they must consider reasonable adjustments. This is the law. What’s considered ‘reasonable’ will depend on your role and the size of the organization.

For example, a large company may be able to offer you a different role with duties that suit you better. However, a small charity might not have other suitable roles.

Examples of reasonable adjustments for a person with disability caused by PKD are:

  • reducing your hours so you’re working part time
  • changing your work pattern so you can avoid rush-hour traffic and have an easier commute
  • letting you work evenings on days you have haemodialysis sessions
  • removing heavy lifting or bending from your duties
  • providing a comfier, more supportive chair
  • letting you work from home when you’re in pain
  • providing a private room for you to do peritoneal dialysis

Be honest with your employer and tell them what would help you.

If your employer doesn’t understand the Equality Act well and they don’t ask about reasonable adjustments, you could make a request in writing. Include points from your medical report. Write down the reasonable adjustments you would like your employer to formally consider. Hopefully, this will get them to act.

4. Work openly with your employer to solve problems

Your employer might not be able to make the reasonable adjustments you or occupational health suggest. If this happens, be open to talking about other ways they can help you.

Example discussion about a reasonable adjustment to hours

Patricia works as a sales manager. Her kidneys don’t work well and this is making her very tired. She asks to reduce her working days from 5 to 4 as a reasonable adjustment. Her employer feels this isn’t possible — they need someone 5 days a week. It would be hard to recruit someone to work the other day.

Example discussion about a reasonable adjustment to hours

Patricia works as a sales manager. Her kidneys don’t work well and this is making her very tired. She asks to reduce her working days from 5 to 4 as a reasonable adjustment. Her employer feels this isn’t possible — they need someone 5 days a week. It would be hard to recruit someone to work the other day.

Patricia and her employer come up with two possible solutions:

  • A junior staff member who is ready to progress could take on a bigger role and hours.
  • Patricia could work 2.5 days. Her employer could recruit another person for the other 2.5 days and set up a job share.

Her employer agrees to look into option 1 first.

A photo of two women talking at a table

5. Know your rights

The Equality Act 2010 and employment law can be hard to understand.

If you’re unsure of your rights on reasonable adjustments, you could ask Citizens Advice in England or Wales or Citizens Advice Scotland.

Or you could ask the Advisory, Conciliation and Arbitration Service (ACAS) to help you and your employer reach an agreement. ACAS helps employers and workers in England, Scotland and Wales. If you’re based in Northern Ireland, the Labour Relations Agency offers a similar service.

What if you’re not classed as disabled but sometimes can’t do your job?

If you’re not classed as disabled, there’s no law to say your employer must make adjustments to help you do your job. However, they might be willing to make changes.

A good place to start is to explain:

  • how PKD is affecting you
  • what would help you to do your job.

It’s possible that you meet the criteria for disability even if you don’t see yourself as disabled. For example, long-term extreme tiredness or difficulty sleeping can count as a disability.

Check the Citizens Advice website to see if you qualify as disabled under the Equality Act 2010. There are separate pages for people in England, Wales, and Scotland. Remember, this act doesn’t apply in Northern Ireland – contact the Quality Commission for Northern Ireland for more information.

Getting sick pay

In England, there are 2 main types of sick pay for employees:

  • Statutory Sick Pay — this is £118.75 per week from day 4 of your sickness up to 28 weeks. It’s paid by your employer.
  • Contractual Sick Pay — this is extra sick pay that some employers offer. Your work contract will have details.

You may also be able to claim sick pay if you’re working reduced hours or days while recovering from surgery or long-term illness.

You can’t get statutory sick pay if you’re self-employed.

You can get statutory sick pay if you work part-time, are on a zero-hours contract or are on a fixed-term contract if:

  • your employer takes tax and national insurance off your pay
  • and you earn at least £125 a week on average

Find out more on the Citizens Advice websites for England, Scotland, and Wales.

What if your sick pay runs out?

If you’ve run out of sick pay, you may be able to claim Employment Support Allowance in England. You can start the claim 3 months before your sick pay is due to run out, as it takes time to set up.

You can also use your holiday pay to cover periods of sickness.

Find out more on the Citizens Advice websites for England.

Support for people in Scotland and Wales differs. 

If you have more time off sick than you’re allowed

Your employer may invite you to a meeting if you have more time off than their absence and sickness policy allows. They could give you a warning about your absence.

Please don’t panic if you’re called to your first meeting about sickness. Your employer may want to understand your PKD and discuss adjustments, which is a good thing.

The action they take regarding your absence will depend, in part, on why you were absent and their absence and sickness policy.

A photo of a man in discomfort, sat on the edge of the bed

To prepare for meetings about absence:

  • When you’re absent due to PKD, make sure that PKD is mentioned in your self-certificate or medical certificate.
  • Know whether you’re classed as disabled in England, Scotland or Wales.
  • Check your company’s absence and sickness policy. Does time off related to disability count as a sick day?
  • Know how many days you have had off for reasons other than PKD.

If your employer is classing your absence related to PKD as sick leave, question this. If you’re classed as disabled, a reasonable adjustment could be to increase the amount of time you can have off for PKD care.

Remember that absences not related to PKD (for example, for a head cold) will count as sick leave.

If your employer issues you a warning for time off related to your PKD, it’s a good idea to seek trade union support (if you’re a trade union member). Alternatively, you could contact ACAS for advice.

When are employers allowed to dismiss an employee?

It’s illegal for companies to discriminate against or mistreat an employee who is disabled. However, there may come a point when your employer feels you’re not able to do your job.

They could take steps to dismiss you if both:

  • They’ve considered all other options
  • Your inability to work is significantly impacting the business

Your employer should show that your dismissal is fair. For example, they could:

  • Show the reasonable adjustments they’ve already made
  • Explain why they can’t make further adjustments
  • Show that the reasonable adjustments made so far aren’t resulting in you meeting your job requirements, which is reducing the amount of money the business is making (profitability)
  • Explain why there isn’t a different role that’s suitable for you

If you’re invited to a disciplinary hearing, you’re allowed to take someone with you if you’d like. This person can be a colleague or a trade union representative.

This is a complex area of law. If you’re in this situation, please seek expert advice, for example, from your trade union or ACAS.

Job hunting

If you’re looking for a new job, your potential future employer can only ask certain things about health and disability. This keeps the selection process fair.

Recruiters can ask:

  • Whether you have a disability that would affect your ability to do a selection assessment (for example, a test at a computer) and what reasonable adjustments they can make to help
  • Whether you can carry out core job functions safely

They might also ask about disability to track the diversity of their job applicants.

Other than these situations, recruiters can’t usually ask questions about your health before offering you a job.

A photo of a person being interviewed at a table

What if you think you’re being unfairly treated?

If you feel that you’re being unfairly treated by your employer due to your PKD, read their grievance procedure. It should explain how to raise concerns. If your employer doesn’t have a grievance procedure, put your concerns in a letter. Write that you’re raising a grievance and give your reasons. Your employer should arrange a meeting with you to discuss your concerns.

If you think you’ve been unfairly treated by a recruiting employer or your current employer, you can lodge a claim with an employment tribunal. You usually need to do this within 3 months of the problem happening.

Before making a claim, you need to tell ACAS. They’ll offer you ‘early conciliation’. This means they’ll talk to you and your employer and try to help you reach an agreement.

If this fails, your claim will go to an employment tribunal. This is similar to a court and is held by a judge. Employment experts without legal powers are often involved too.

The tribunal will hear evidence from you and your employer. They’ll decide whether you’re owed compensation (money).

Please get suitable advice, for example from your trade union or ACAS. They can help you take the right steps.

Benefits for people who are sick or disabled

If you need extra help because of an illness, disability or mental health condition, you might be able to get disability benefits.

Find out more on the Citizens Advice website for England, Scotland and Wales.

Information and support from others

England, Scotland and Wales

Northern Ireland

The photos on this webpage are freely available on Pexels.com. The medical history of the persons shown is unknown. 

Further Information

All of our publications are based on references but these are removed for ease of reading on our webpages. A version of this webpage with references included is available upon request by emailing [email protected]

Authors and contributors

Originally written by Fiona Davies in 2020. Updated and adapted in 2025 by Hannah Bridges, PhD, Independent Medical Writer, HB Health Comms Limited. Expert review by Sarah Borrows, Clinical Nurse Specialist Renal Genetics, Queen Elizabeth Hospital, Birmingham. 

With thanks to all those affected by PKD who contributed to this publication.

Ref No: ADPKD.AE.V2.0

Last Updated: © September 2025 (v2.0).

Due for medical review: September 2028.

Disclaimer: This information is primarily for people in the UK. We have made every effort to ensure that the information we provide is correct and up to date. However, it is not a substitute for professional medical advice or a medical examination. We do not promote or recommend any treatment. We do not accept liability for any errors or omissions. Medical information, the law and government regulations change rapidly, so always consult your GP, pharmacist or other medical professional if you have any concerns or before starting any new treatment.

If you don't have access to a printer and would like a printed version of this information sheet, or any other PKD Charity information, call the PKD Charity Helpline on 0300 111 1234 (weekdays, 9am–5pm) or email [email protected]

The PKD Charity Helpline offers confidential support and information to anyone affected by PKD, including family, friends, carers, newly diagnosed or those who have lived with the condition for many years.

Read more …Employment advice

Appointment tips ADPKD

Appointment tips

These tips are for people with autosomal dominant polycystic kidney disease (ADPKD), their families and caregivers. They’re to help you get the most out of appointments with your doctor, kidney specialist and other healthcare professionals.

Health appointments can be stressful and worrying at times. You might sometimes come away confused or realize that you didn’t ask the questions you planned to.

Our check lists and example questions below can help you to feel confident and get the most out of appointments. This will help you to get the care, support and information you need to manage your health well.

Contents

Check list: Before the appointment

❑ Are you happy with the appointment plans? If not, request changes.

  • If you want to see a particular healthcare professional, call to ask.
  • If you’ve been given a telephone or video appointment but would prefer to see someone in person, ask whether this can be changed. Likewise, it’s sometimes possible to swap a face-to-face appointment to a call or video.
  • You might also be able to change the appointment day or time if it isn’t convenient but this might mean the date is later.
  • If you need an interpreter, ask right away.

❑ Write down your symptoms and any treatment side effects.

  • How long have you had them?
  • How bad are they?
  • What makes them better or worse?
  • How are they affecting your life?

❑ Make a list of the questions you want to ask.

  • Put the most important ones first.
  • If you have a lot to discuss, ask for a longer appointment.
  • For a list of example questions, see later on this page.

❑ Check whether you can take someone along if you’d like to.

  • A friend or family member could help you feel confident. They can also help you pace the conversation, remember your questions and take notes. However, some clinics might not always allow this.

❑ Plan the trip so you don’t end up rushing.

  • How will you get to the surgery or hospital?
  • Where are the nearest public transport stops?
  • If driving, is there parking and what’s the cost?
  • If you have access needs, ask for the support you need right away.

❑ For video and phone appointments, plan to be somewhere quiet, private and with a good signal.

  • Make sure your phone and computer have enough battery.
  • For video calls, check you have the invite link and do a test run if possible.
  • Is there a number you can call for technical support?

❑ If you’re going to have a test or procedure, make sure you understand what will happen.

  • Read the letter carefully and follow the instructions given (such as not eating or drinking before the appointment).
  • Contact the clinic beforehand if you’re unsure of anything. If contact details are not on your letter, call the main phone number for the hospital or surgery and ask to be put through to the department you’re due to visit.

❑ Collect any information requested.

  • When you see a specialist for the first time, they may want your medical history and that of your family.
  • Make a list of the names and doses of any medicines, supplements and vitamins you take. If easier, you could take photos of your medicines or take the packets with you.
  • If you have extra information to share, get this ready. For example, home blood pressure checks or weight records.

❑ Pack drinks and snacks.

  • If you might be waiting a long time for or between appointments, take drinks and snacks.

Check list: At the appointment

❑ Explain that you have some notes you’ll be using.

  • Start with the most important points and tick things off as you go.

❑ Be open and honest about your symptoms and concerns.

  • This might mean discussing things you find embarrassing. Don’t leave them until the last minute.

❑ Write down key details.

  • It’s easy to forget details after an appointment, so write things down.
  • If you prefer, ask if you can record the discussion on your phone.
  • Some video call systems allow you to record the discussion (remember to ask first).
  • You can also ask the doctor, nurse or pharmacist to print out useful information or provide a copy of your notes, reports and letters.

❑ If anything isn’t clear, ask for it to be repeated or explained differently.

  • Some healthcare professionals are better at explaining things than others.
  • If you’re confused, say so.
  • You could also ask for a leaflet or a website to learn more.

❑ Ask about the benefits and side effects of treatments.

  • For example, how might the procedure or treatment help you?
  • How serious and common are side effects and risks?
  • How can side effects and risks be reduced?
  • Are there other treatment options?

❑ Check when and how you’ll get test results.

  • Who can you contact if you don’t receive a letter or phone call when expected?

❑ Who can you contact with questions?

  • Is there a doctor, nurse or other healthcare professional you can contact by phone or email if you have questions?
  • Alternatively, how can you book a follow-up appointment?

Check list: Pause for thought

❑ If you need a minute or two to think things through, say so.

  • For video calls, you could turn off your camera for a moment if this is more comfortable.

❑ Check your notes.

  • Have you covered everything?
  • If you’re out of time but have more questions, ask for a follow-up appointment.

❑ Repeat key points back to the healthcare professional to check you understand correctly.

Check list: Follow up

❑ Write down any questions you have after your appointment.

  • You may be able to ask them by phone, video call or by email.
  • Or you could request a follow-up appointment.

❑ If your symptoms worsen or you have side effects, tell a healthcare professional.

  • Don’t wait for the next check-up if it’s not soon.

❑ If you don’t receive test results or a referral when expected, call the surgery or hospital.

  • Sometimes, results or referrals are delayed or overlooked. A gentle reminder can help.

❑ If you’re unhappy about the care you’ve received, give feedback or make a complaint.

  • It’s your choice whether you do this, but it can help services improve.
  • For GP surgeries, you could contact the Practice Manager or ask the receptionist how you can give feedback or complain.
  • For hospitals, you could contact their Patient Advice and Liaison Service (PALS).

Questions to ask at kidney check-ups

Here are some of the example questions people ask at kidney check-ups.

About your test results

  • Has my kidney function changed?
  • How quickly is my disease progressing? (When might I need to have dialysis or a transplant?)
  • Is my blood pressure healthy?
  • Do my test results show any other changes?
  • Can you explain what this word/result means?
  • Do we need to make any changes to my treatment?
  • When is my next check-up?

About treatments

  • What are my treatment options?
  • What are the benefits, side effects and risks of each treatment option?
  • Are there any risks to my health if I don’t go ahead with treatment?
  • Are any serious side effects possible?
  • What side effects should I look out for?
  • What should I do if I get side effects?
  • How often should I take my medicine and what is the right dose?
  • What should I do if I forget to take my medicine at the right time?

About your quality of life

  • What can help to lessen the symptoms or side effects I’ve got?
  • How can we improve my quality of life?
  • What support might I need from friends and family?
  • Could I improve my diet or lifestyle?
  • Where can I get more information or support? You could ask for a referral to a genetics counsellor, dietitian, counsellor, psychologist or pain specialist if you think this would help you.

More from the PKD Charity

Information and support from others

Kidney Care UK has a good explanation of blood and urine test results.

Further information

All of our publications are based on references but these are removed for ease of reading on our webpages. A version of this webpage with references included is available upon request by emailing [email protected]

Authors and contributors

Written by Hannah Bridges, PhD, medical writer, HB Health Comms Ltd. Expert review by Sarah Borrows, Clinical Nurse Specialist Renal Genetics, Queen Elizabeth Hospital, Birmingham.

With thanks to all those affected by PKD who contributed to this publication.

Ref No: ADPKD.AT.V2.0
© PKD Charity 2025
First published: June 2025
Due to be medically reviewed: June 2028

Disclaimer: This information is primarily for people in the UK. We have made every effort to ensure that the information we provide is correct and up to date. However, it is not a substitute for professional medical advice or a medical examination. We do not promote or recommend any treatment. We do not accept liability for any errors or omissions. Medical information, the law and government regulations change rapidly, so always consult your GP, pharmacist or other medical professional if you have any concerns or before starting any new treatment.

If you don't have access to a printer and would like a printed version of this information sheet, or any other PKD Charity information, call the PKD Charity Helpline on 0300 111 1234 (weekdays, 9am–5pm) or email [email protected].

The PKD Charity Helpline offers confidential support and information to anyone affected by PKD, including family, friends, carers, newly diagnosed or those who have lived with the condition for many years.
Read more …Appointment tips ADPKD

Being pregnant with ADPKD

Being pregnant with ADPKD

This information is for women with autosomal dominant polycystic kidney disease (ADPKD) who are pregnant. It’s also for their partner, family and friends. It explains the care you should receive when pregnant with ADPKD to keep you and your baby safer. If you’re not yet pregnant, please also read our page on planning a pregnancy.  

If reading about the risks of pregnancy causes you any worry, our helpline is available on 0300 111 1234, Facebook Messenger and by email on [email protected]

Contents

Key facts

  • Most women with ADPKD have successful pregnancies. 
  • If you have ADPKD, your chance of having some problems during pregnancy may be higher than other women.  
  • The less well your kidneys work, the greater the chance of problems.  
  • Problems can include high blood pressure, pre-eclampsia (where your blood pressure gets dangerously high) and urinary tract infections. 
  • Treatments are available for these problems. 
  • If your kidneys don’t work well, your baby is more likely to grow slowly. They could be born a low weight, be born early, and need care in a special unit. 
  • If you want, you could have your developing baby (fetus) tested for ADPKD early in pregnancy. 
  • As well as the usual care during pregnancy (antenatal care), you may have extra check-ups, scans and tests.  
  • This means your midwife and doctors can spot any problems early and give you and your baby the care you need.  
  • The amount that pregnancy could affect your kidneys depends, in part, on how well your kidneys work currently. 

What do I do once pregnant?

Let your GP know when you’re pregnant. They’ll refer you to services for pregnant women (antenatal services). You can contact the antenatal service directly if you prefer.  

Also tell your kidney doctor that you’re pregnant. 

If you’re taking any medicines, see your GP or kidney doctor as soon as possible. They’ll make any changes to your medicines that are needed.  

How might ADPKD affect my pregnancy?

If you have ADPKD, your chance of having some problems during pregnancy may be higher than other women. The worse your kidneys work, the greater the chance of problems. We explain some of these problems below. 

Some problems during pregnancy could affect your health or your baby’s. However, most problems can be managed with treatment and careful monitoring.  

Most women with ADPKD have successful pregnancies. This includes women with ADPKD who have had a kidney transplant. 

Your pregnancy care team (antenatal team) will monitor you carefully throughout your pregnancy. This means they can pick up any problems quickly and get you the right treatment.  

Pregnant woman's torso with hands on tummy forming a love heart

Miscarriage 

Loss of a pregnancy before week 23 is called miscarriage. Miscarriage is common in the UK. It happens in about 15 out of every 100 pregnancies in the general population. 

We are not sure whether having ADPKD affects your chance of having a miscarriage.  

Studies have shown that women with chronic kidney disease have a higher risk of miscarriage. However, many women with ADPKD at childbearing age have kidneys that work quite well. So, the results of studies in chronic kidney disease might not be relevant to all women with ADPKD.   

You can learn more about miscarriage on the Tommy’s website - Tommy’s is a charity that provides information on miscarriage and pregnancy.  

Blood pressure problems 

If you have ADPKD, you’re more likely to get blood pressure problems during your pregnancy than other women.  

This is why your blood pressure should be monitored during pregnancy. 

  • If you already have high blood pressure, this could worsen during pregnancy. 
  • If you don’t have high blood pressure, you could develop it during pregnancy (this is called gestational hypertension). 
  • You could get a problem called pre-eclampsia, where your blood pressure gets very high. This can be dangerous for you and your baby. 

You’re more likely to get pre-eclampsia if your kidneys don’t work well. 

Most women with high blood pressure and pre-eclampsia have successful pregnancies. However, these conditions need careful management to keep you and your baby safe.  

Very high blood pressure caused by pre-eclampsia usually reduces within days of birth. 

Urinary tract infections 

Women with ADPKD are more likely to get urinary tract infections while pregnant than other women. These infections sometimes travel to the kidneys.  

If you get an infection, you’ll need antibiotics to treat it. 

Effects on the baby 

If your kidneys don’t work well (low kidney function), your baby is more likely to: 

  • grow slowly or be born a low weight  
  • be born early (premature birth)  
  • need care in a special unit (a neonatal unit) after birth 

A recent study looked at over 1600 pregnant women with ADPKD in the UK. These women were not on dialysis, had not had a transplant, and most had near normal kidney function. Fewer than 2 in every 10 women (17%) had a premature baby (birth before 37 weeks). (A full-length pregnancy is about 40 weeks.) 

A different study looked at pregnant women with ADPKD who had low or very low kidney function. About 7 in every 10 women (70%) had a premature baby (birth before 37 weeks). The women with high blood pressure were most likely to have a premature baby.  

Premature babies often need special care in a neonatal unit. You can find out more about specialist neonatal care on the NHS website. 

Medicines in pregnancy

Which medicines can be a problem during pregnancy?

Some medicines are unsafe to use during pregnancy. They could harm your growing baby in the womb.15 We list some of these medicines in the table below.  

Ask your doctor to review your medicines before you get pregnant. If you’re already pregnant, ask for a review right away.  

Never stop taking medicines without talking to a doctor first as this could put you or your baby at risk.  

You might need to swap to a different medicine, rather than stopping treatment. For example, women taking medicine for high blood pressure usually swap to a different medicine during pregnancy. This ensures that their blood pressure is still controlled, which is important for pregnancy.  

Medicines that your doctor may advise you to stop or swap during pregnancy 

Medicines to reduce cyst growth 

  • Tolvaptan (Jinarc® 

Medicines to control blood pressure 

  • Angiotensin converting enzyme inhibitors (ACE inhibitors): captopril, enalapril, fosinopril, imidapril, lisinopril, moexipril, perindopril, quinapril, ramipril and trandolapril 
  • Angiotensin-II receptor blockers (ARBs): azilsartan, candesartan, eprosartan, irbesartan, losartan, olmesartan, telmisartan and valsartan  
  • Thiazide-like diuretics: chlortalidone, indapamide, metolazone and xipamide  

Medicines to treat overactive parathyroid glands 

  1. Calcimimetics: cinacalcet and etelcalcetide 

Medicines to treat high phosphate levels 

  1. Non-calcium-based phosphate binders: sevelamer, lanthanum and sucroferric oxyhydroxide 

Antibiotics 

  • Erythromycin and clarithromycin if you’re also taking the immunosuppressant tacrolimus or ciclosporin 

Immunosuppressants (used after kidney transplant) 

  • Mycophenolate mofetil, methotrexate, cyclophosphamide, sirolimus and everolimus 
  • Rituximab (if a different medicine is suitable for you) 

What happens at antenatal services?

Care for pregnant women up until birth is called antenatal care. 

You’re likely to see a midwife at your first appointment at the antenatal clinic.  

The midwife will:  

  • collect the information from you that the service needs to plan your care 
  • offer you a pregnancy check-up  
  • explain what care you’ll have until birth 

Tell the midwife about your ADPKD so they can organize the right care team for you. 

Your care for the rest of your pregnancy is likely to be with a specialist team including: 

  • a pregnancy doctor (obstetrician) 
  • midwives experienced in looking after women with medical conditions 
  • a kidney doctor (nephrologist)  

Later in your pregnancy, you may have more antenatal appointments than standard. These are to monitor you and your baby. You might also be offered extra scans, depending how your pregnancy is going. 

Someone is always on hand at the antenatal service should you have any concerns during pregnancy. 

Testing for ADPKD during pregnancy

If you or your partner have ADPKD, there’s a 1 in 2 (50%) chance of your baby having ADPKD. This risk is the same for each child you have. 

Testing for ADPKD before pregnancy is called pre-implantation genetic testing. We explain it on our web page on planning a pregnancy 

You can also have your developing baby (fetus) tested for ADPKD in the womb. This is called chorionic villus sampling; see our page on planning a pregnancy for more inforamtion. It’s done at weeks 11–14 of pregnancy.  

To do the test, your pregnancy doctor will take a sample of cells from the placenta. This is usually done by putting a needle through your abdomen (tummy). 

There’s a small risk of the test leading to miscarriage. This happens in fewer than 1 in every 200 women.  

Doctors only recommend chorionic villus sampling when the results would help you decide whether to end a pregnancy.  

See the NHS website for more on: 

 Our helpline is available on 0300 111 1234, Facebook Messenger and email ([email protected]) for emotional support. 

The charity Antenatal Results and Choices has a helpline for people considering the results of these tests. Call 0207 713 7486 or text 07908 683004. 

Will I need extra check-ups during pregnancy? 

You should have extra tests during pregnancy because you have ADPKD.  

These may include: 

  • frequent checks of your blood pressure (your doctor may suggest doing checks at home) 
  • blood tests to check how well your kidneys work (your kidney function) 
  • urine tests to check protein levels in your urine 
  • urine tests to check for urinary tract infections 
  • blood tests for pre-eclampsia  

Go to all your check-ups. Your midwife and doctors can then spot any problems early and give you and your baby the care you need.  

The usual measure of kidney function (estimated glomerular filtration rate or eGFR) is not used during pregnancy. eGFR is not accurate in pregnant women. Your kidney doctor will measure your creatinine levels instead.  

How is blood pressure controlled during pregnancy? 

Control of blood pressure is important during pregnancy. It reduces your chance of getting pre-eclampsia and so keeps you and your baby safer. 

Women with ADPKD are more likely to have high blood pressure during pregnancy than other women. It’s most likely to happen in the last few months of pregnancy. 

Your antenatal team will measure your blood pressure often. They may suggest you measure it at home too. 

If your blood pressure is high, medicines can help. Examples of ones used during pregnancy are labetalol, nifedipine, methyldopa, clonidine and oxprenolol. Your doctor will talk you through the best options. 

Staying a healthy weight, exercising and eating healthy food are also good for blood pressure.

A photo of a woman having a blood pressure reading

What happens if I get pre-eclampsia? 

Pre-eclampsia can occur in the last few months of pregnancy or after birth. It causes a sudden rise in blood pressure. Most women with pre-eclampsia don’t get serious problems, but a few do. It can affect the growth of your baby. 

Women with ADPKD are more likely to get pre-eclampsia than other women: 

  1. Of 100 pregnant women in the general population, up to 5 will get pre-eclampsia  
  1. Of 100 pregnant women with ADPKD, about 9 will get pre-eclampsia 

Your risk of pre-eclampsia may be higher if your kidneys don’t work well or your blood pressure is high. 

Your antenatal team may suggest that you take aspirin at a low dose (75–150 mg) from week 12 to week 36. This reduces your risk of pre-eclampsia. 

They may also offer you blood tests for pre-eclampsia.  

If you get pre-eclampsia, you’ll need extra monitoring and care in hospital. The main treatments for pre-eclampsia are to manage your blood pressure safely and to plan the birth for the best time.  

Doctors may recommend you give birth a few weeks early. The timings depend on when pre-eclampsia occurs. They’ll organize the care you’ll need for this.  

Very high blood pressure caused by pre-eclampsia usually reduces within days of giving birth. 

Learn more about pre-eclampsia on the Tommy’s website. 

What other treatments might I need? 

If you have too few red blood cells (anaemia) during pregnancy, you might need iron injections or an erythropoietin stimulating agent (EPO). These are safe to use during pregnancy.  

If your levels of vitamin D are low, you may need vitamin D supplements. 

How do we plan for the birth? 

Your antenatal team will help you to plan for the birth. They’ll make sure any extra care needed for you and your baby is in place. 

See our web page on giving birth for more information. 

Where can I get practical and emotional support? 

For information, practical advice and emotional support from people with experience of ADPKD, ring our confidential PKD Helpline 0300 111 1234. We’re open 9:30am to 5:00pm, Monday to Friday, except bank holidays. 

You can connect with other people with ADPKD via our Facebook group or PKD support groups. 

The charities Tommy’s and the National Childbirth Trust (NCT) also offer advice on pregnancy, birth, miscarriage, caring for babies, and more.  

A private doula can also provide practical advice and emotional support. Doulas are not medically trained but have experience of how to help people through pregnancy, birth and afterwards. Find out more on the Tommy’s website. 

Will being pregnant harm my kidneys?

Pregnancy can cause some damage to your kidneys. 

If your kidney function is medium (chronic kidney disease stage 3), having a baby could slightly affect your kidneys. The damage is about the same as ADPKD would usually cause over 2 years. 

If your kidney function is poor (chronic kidney disease stage 4 or 5), having a baby could affect your kidneys quite a bit. The damage is about the same as ADPKD would usually cause over 5 years. 

If you get high blood pressure during pregnancy, your kidneys are more likely to get some damage. 

Your kidney doctor can explain: 

  • how pregnancy might affect your kidney health 
  • how you can reduce risks 
  • signs of kidney problems to look out for 
  • treatments to help  

Will being pregnant harm my liver?

Many women with ADPKD have cysts in their liver. This is known as polycystic liver disease (PLD).  

Pregnancy can increase the growth of liver cysts. However, experts think pregnancy doesn’t increase your chance of having serious problems from PLD. There’s not been much research on this, so we can’t be sure.  

Will my ADPKD affect how well I can parent?

Having ADPKD won’t stop you being a good parent.  

You might need more support with childcare if you’re unwell or having treatment.   

Ask your kidney doctor to explain how your ADPKD may affect your health as you get older. 

Chat with your partner, family and friends about any worries. Having their support and putting plans in place can be reassuring.  

You may find it helpful to talk to other parents with ADPKD. You can connect with them through our Facebook group or support groups.More information from the PKD Charity 

  • Planning a pregnancy if you have ADPKD 
  • Giving birth if you have ADPKD 

Useful information from others 

  • The National Childbirth Trust has information pregnancy. 
  • Antenatal Results and Choices has a helpline for people whose unborn baby has been diagnosed with a condition. Call 0207 713 7486 or text 07908 683004. 

Authors and contributors

Written by Hannah Bridges, independent medical writer, HB Health Comms Limited. Reviewed by Dr Mairéad Hamill, Nephrology Specialist Registrar, Kings College London, London, UK. 

This page was adapted from an earlier version written by Dr Kate Bramham, Consultant Nephrologist and Olivia Snowball, Research Midwife. 

With thanks to all the people affected by ADPKD who contributed to this publication. 

Ref No: ADPKD.BEP.V4 
© PKD Charity 2026 
First published: August 2026 
Due to be medically reviewed: August 2029 
 

Disclaimer: This information is primarily for people in the UK. We have made every effort to ensure that the information we provide is correct and up to date. However, it is not a substitute for professional medical advice or a medical examination. We do not promote or recommend any treatment. We do not accept liability for any errors or omissions. Medical information, the law and government regulations change rapidly, so always consult your GP, pharmacist or other medical professional if you have any concerns or before starting any new treatment. 

If you don't have access to a printer and would like a printed version of this information sheet, or any other PKD Charity information, call the PKD Charity Helpline on 0300 111 1234 (weekdays, 9am–5pm) or email [email protected] 

The PKD Charity Helpline offers confidential support and information to anyone affected by PKD, including family, friends, carers, newly diagnosed or those who have lived with the condition for many years. 

 

Feedback 

We welcome feedback on the information provided on this webpage. If you have any feedback regarding the information provided on this webpage, please complete the Feedback Form. 

Read more …Being pregnant with ADPKD

Giving birth with ADPKD

Giving birth with ADPKD 

This information is for women with autosomal dominant polycystic kidney disease (ADPKD) who are planning the birth of their baby. It’s also for their partner, family and friends. It explains the extra care that is available during birth to help keep you and your baby safer. We also have web pages on planning a pregnancy and being pregnant.  

If reading about the risks of birth causes you any worry, our helpline is available on 0300 111 1234, Facebook Messenger and by email on [email protected]

Contents

Key facts

  • You can choose where you give birth. 
  • Your pregnancy care team (antenatal team) will explain the pros and cons of different settings. 
  • Your pregnancy doctor (obstetrician) may advise you to give birth in hospital if your kidneys don’t work well. 
  • They might also advise this if you have high blood pressure, pre-eclampsia or have had other pregnancy problems. 
  • Your midwife or obstetrician will monitor your baby during your labour. 
  • They may offer extra monitoring for your baby’s heart. 
  • Some but not all women with ADPKD have surgery (a caesarean) to deliver the baby. 
  • Your midwife or obstetrician will explain different types of pain relief for labour and birth. 
  • If your kidneys don’t work well, some pain killers might not be suitable for you, or you may need a lower dose.  
  • You should have a check-up with your kidney specialist within 6 months of giving birth. 

Where will I give birth? 

You can choose where you give birth. This could be at home, at a birth centre led by midwives, or in the hospital. For more information on these options, see the Tommy’s website. Tommy's are a charity that provide information and support around pregnancy.  

Your antenatal team will explain the pros and cons of different settings. This depends partly on how your pregnancy has gone and any previous births you’ve had. 

Your pregnancy doctor (obstetrician) may advise you to give birth in hospital if your kidneys don’t work well. They might also advise this if you have high blood pressure, pre-eclampsia or have had other pregnancy problems. 

Hospitals are best equipped to monitor you and your baby closely. They can quickly give you any extra care needed.  

Your antenatal team should respect your choices for the birth. 

A photo of a couple looking at their newborn baby

How will our baby be monitored during labour and birth? 

Your midwife or obstetrician will monitor your baby during your labour. They may offer extra monitoring for your baby’s heart. This is called continuous cardiotocography (CTG).  

CTG allows midwives and doctors to see your baby’s heart rate. If there are any signs of problems, they can give you and your baby the care you need right away.  

What type of delivery will I have? 

Your obstetrician will talk you through options for your baby’s delivery.  

The two options are: 

  • giving birth through your vagina  
  • having surgery (a caesarean or ‘C-section’)  

You can learn about types of delivery on the Tommy’s website.  

Your obstetrician will explain the pros and cons of each option. 

If you’ve had some problems during pregnancy, your obstetrician might recommend you give birth early. This could be 1 or 2 weeks before your due date, for example.  

If you have the baby early options are: 

  • a caesarean 
  • using medicines or devices to start your labour (induction) 

Some but not all women with ADPKD have a caesarean.  

If you or a close relative have had a brain aneurysm, your obstetrician might recommend a caesarean.  

What options will I have for pain relief during labour and birth? 

Your midwife or obstetrician will explain different types of pain relief for labour and birth. They’ll offer all options unless there’s a reason some wouldn’t be suitable. 

You can choose to give birth without medicines for pain relief if you prefer.  

Options for pain relief include: 

  • a machine that uses a small electric current to reduce pain, called a transcutaneous electrical nerve stimulation (TENS) machine 
  • injections of strong pain killers (pethidine and diamorphine) 
  • breathing a mix of nitrous oxide gas and air (Entonox®) 
  • an injection of numbing medicine (anaesthetic) into your spine, which is called an epidural 

If your kidneys don’t work well, some pain killers might not be suitable for you, or you may need a lower dose.  

Using a birthing ball or giving birth in water might help to ease pain a little.  

Which pain killers can I use after the birth? 

Ask your doctor which pain killers you can use after the birth. 

  • Don’t take non-steroidal anti-inflammatory drugs (NSAIDS), such as ibuprofen (Nurofen®) or diclofenac (Voltarol®) unless your doctor says this is okay. These medicines can harm your kidneys.  
  • You can use paracetamol even if you’re breastfeeding. 
  • Don’t take codeine if you’re breastfeeding.  

Can I breastfeed? 

If you want to breastfeed, check with your GP or kidney doctor that this is safe with any medicines you take. If any medicines would be a problem, you might be able to change them.

How can we find out whether our baby has ADPKD?  

Unless you have had pre-implantation genetic testing (PGT) or chorionic villus sampling, you won’t know whether your baby has ADPKD before they’re born. We explain these tests on our webpage on planning a pregnancy. 

It’s uncommon for signs of ADPKD to show up on scans during pregnancy. Most children with ADPKD don’t have symptoms until they’re older. 

Children can be tested for ADPKD if either parent has the condition. 

The two types of test are: 

  • a kidney scan 
  • a genetic test to look for a gene causing ADPKD  

You can find out about these tests on our webpage Symptoms of ADPKD and tests in children. 

Do I need a kidney check-up after birth? 

You should have a check-up with your kidney specialist within 6 months of giving birth.  

They’ll check your kidney function and blood pressure. They’ll suggest changes to any blood pressure medications you take, if needed, to control your blood pressure better.   

Where can I get practical and emotional support? 

For information, practical advice and emotional support from people with experience of ADPKD, ring our confidential PKD Helpline 0300 111 1234. We’re open 9:30am to 5:00pm, Monday to Friday, except bank holidays. 

You can connect with other people with ADPKD via our Facebook group or PKD support groups. 

The charities Tommy’s and the National Childbirth Trust (NCT) also offer advice on pregnancy, birth, miscarriage, caring for babies and more.  

A private doula can also provide practical advice and emotional support. Doulas are not medically trained but have experience of how to help people through pregnancy, birth and afterwards. Find out more on the Tommy’s website. 

Will my ADPKD affect how well I can parent? 

Having ADPKD won’t stop you being a good parent.  

You might need more support with childcare if you’re unwell or having treatment.   

Ask your kidney doctor to explain how your ADPKD may affect your health as you get older. 

Chat with your partner, family and friends about any worries. Having their support and putting plans in place can be reassuring.  

You may find it helpful to talk to other parents with ADPKD. You can connect with them through our Facebook group or support groups.

More information from the PKD Charity 

Useful information from others 

  • Tommy’s (a pregnancy and baby charity) has lots of information on giving birth. 
  • The NHS website has information on birth. 

Authors and contributors

Written by Hannah Bridges, independent medical writer, HB Health Comms Limited. Reviewed by Dr Mairéad Hamill, Nephrology Specialist Registrar, Kings College London, London, UK. 

This page was adapted from an earlier version written by Dr Kate Bramham, Consultant Nephrologist and Olivia Snowball, Research Midwife. 

With thanks to all the people affected by ADPKD who contributed to this publication. 

Ref No: ADPKD.BEP.V4 
© PKD Charity 2026 (Charity no: 1160970)
First published: August 2026 
Due to be medically reviewed: August 2029 
 

Disclaimer: This information is primarily for people in the UK. We have made every effort to ensure that the information we provide is correct and up to date. However, it is not a substitute for professional medical advice or a medical examination. We do not promote or recommend any treatment. We do not accept liability for any errors or omissions. Medical information, the law and government regulations change rapidly, so always consult your GP, pharmacist or other medical professional if you have any concerns or before starting any new treatment. 

If you don't have access to a printer and would like a printed version of this information sheet, or any other PKD Charity information, call the PKD Charity Helpline on 0300 111 1234 (weekdays, 9am–5pm) or email [email protected] 

The PKD Charity Helpline offers confidential support and information to anyone affected by PKD, including family, friends, carers, newly diagnosed or those who have lived with the condition for many years. 

Read more …Giving birth with ADPKD

Planning a pregnancy if you have ADPKD

Planning a pregnancy if you have ADPKD

This information is for people with autosomal dominant polycystic kidney disease (ADPKD) who are thinking of having a baby. It’s also for their family and friends. It answers questions you’re likely to have, such as whether you can get pregnant or will your baby have ADPKD? Also, what extra steps help to look after you and your baby’s health? We have separate pages on being pregnant and giving birth.

If reading about the risks of pregnancy causes you any worry, our helpline is available on 0300 111 1234, Facebook Messenger and by email on [email protected].

Contents

Key facts

  • It’s a good idea to talk to your GP and kidney doctor before trying to get pregnant.
  • They can explain any extra care you might need and check whether you need to stop or swap any medicines.
  • How well women’s kidneys work can affect how easily they get pregnant (their fertility).
  • ADPKD doesn’t usually affect men’s fertility but may cause difficulties with sex.
  • If you and your partner are having problems getting pregnant, fertility services and other treatments can often help.
  • Most women with ADPKD have successful pregnancies.
  • If you have ADPKD, your chance of having some problems during pregnancy may be higher than other women.
  • Treatments are available for these problems.
  • If your kidneys don’t work well, your baby is more likely to grow slowly. They could be born a low weight, be born early and need care in a special unit.
  • If you want to be sure you have a baby without ADPKD, you might be able to have a special type of in vitro fertilization (IVF) where your embryos are tested for ADPKD.
  • Another option is to have your developing baby (fetus) tested for ADPKD early in pregnancy.
  • The amount that pregnancy could affect your kidneys depends, in part, on how well they work currently.
  • Your alternatives to pregnancy may include surrogacy or adoption.

Can women with ADPKD get pregnant?

How well your kidneys work may affect how easily you can get pregnant (your fertility).

If your kidneys work quite well, ADPKD probably won’t affect your fertility.

If your kidneys don’t work well, it might be harder to get pregnant. You may have low levels of some hormones in your body. This means your ovaries are less likely to release an egg each month (ovulate).

If you’re not having success getting pregnant, ask your GP (doctor) to refer you to a fertility specialist. They can look into why and talk you through options to help.

In vitro fertilization (IVF) helps many people with kidney disease to have a baby. It has a few risks.1 Ask the fertility specialist to explain these.

Find out how IVF works on the Tommy’s website. Tommy's are a charity that provide information and support around pregnancy.

Photo of a couple holding a pregnancy test stick.

Can men with ADPKD father children?

ADPKD doesn’t usually affect men’s fertility (the chance of their sperm fertilizing an egg).

Some men with ADPKD have cysts in the tubes that carry semen and sperm.3 ADPKD can also affect sperm (for example, reducing how well sperm can swim).

Despite these changes, most men with ADPKD are probably fertile. There hasn’t been much research on this so we can’t be sure.

Men whose kidneys don’t work well (chronic kidney disease) often have problems getting or keeping an erection. Some may have less interest in sex or have problems ejaculating (‘coming’).

If you’re trying for a baby and aren’t having success, speak to your GP. Changing your kidney treatments or using treatments for erection problems may help. Your doctor can also arrange for you to see a fertility specialist or suggest counselling to work through sexual issues.

How might ADPKD affect my pregnancy?

If you have ADPKD, your chance of having some problems during pregnancy may be higher than other women. The worse your kidneys work, the greater the chance of problems. We explain some of these problems below.

Some problems during pregnancy could affect your health or your baby’s. However, most problems can be managed with treatment and careful monitoring.

Most women with ADPKD have successful pregnancies. This includes women with ADPKD who have had a kidney transplant.

Before getting pregnant, speak to your kidney doctor (nephrologist) about how your ADPKD might affect pregnancy. Also ask your GP to refer you to a pregnancy specialist (obstetrician) for advice. 

A team of pregnancy experts called an antenatal team will monitor you carefully throughout your pregnancy. This means they can pick up any problems quickly and get you the right treatment.

Miscarriage

Loss of a pregnancy before week 23 is called miscarriage. Miscarriage is common in the UK. It happens in about 15 out of every 100 pregnancies in the general population.

We are not sure whether having ADPKD affects your chance of having a miscarriage.

Studies have shown that women with chronic kidney disease have a higher risk of miscarriage. However, many women with ADPKD at childbearing age have kidneys that work quite well. So, the results of studies in chronic kidney disease might not be relevant to all women with ADPKD. 

You can learn more about miscarriage on the Tommy’s website.

Blood pressure problems

If you have ADPKD, you’re more likely to get blood pressure problems during your pregnancy than other women. This is why your blood pressure should be monitored during pregnancy.

  • If you already have high blood pressure, this could worsen during pregnancy.
  • If you don’t have high blood pressure, you could develop it during pregnancy (this is called gestational hypertension).
  • You could get a problem called pre-eclampsia, where your blood pressure gets very high. This can be dangerous for you and your baby.

You’re more likely to get pre-eclampsia if your kidneys work poorly.

Most women with high blood pressure and pre-eclampsia have successful pregnancies. However, these conditions need careful management to keep you and your baby safe.

Very high blood pressure caused by pre-eclampsia usually reduces within days of giving birth.

Urinary tract infections

Women with ADPKD are more likely to get urinary tract infections while pregnant than other women. These infections sometimes travel to the kidneys.

If you get an infection, you’ll need antibiotics to treat it.

Effects on the baby

If your kidneys don’t work well (low kidney function), your baby is more likely to:

  • grow slowly or be born a low weight
  • be born early (premature birth)
  • need care in a special unit (a neonatal unit) after birth

A recent study looked at over 1600 pregnant women with ADPKD in the UK. These women were not on dialysis, had not had a transplant and most had near normal kidney function. Fewer than 2 in every 10 women (17%) had a premature baby (birth before 37 weeks). (A full-length pregnancy is about 40 weeks.)

A different study looked at pregnant women with ADPKD who had low or very low kidney function. About 7 in every 10 women (70%) had a premature baby (birth before 37 weeks). The women with high blood pressure were most likely to have a premature baby.

Premature babies often need special care in a neonatal unit. You can find out more about specialist neonatal care on the NHS website.

Will our baby have ADPKD?

If you or your partner have ADPKD, there’s a 1 in 2 (50%) chance of your baby having ADPKD. This risk is the same for each child you have.

ADPKD is caused by a gene change:

  • If your baby inherits the changed gene from the parent with ADPKD, they’ll have ADPKD.
  • If your baby inherits a healthy gene from both parents, they won’t have ADPKD.

Find out more about how ADPKD is passed to children on our page Genetic testing and counselling for ADPKD.

Are there ways to have a baby without ADPKD?

If you or your partner have ADPKD and you want a baby without the condition, your options may include:

  • If the man has ADPKD, you could use a sperm donor.
  • If the woman has ADPKD, you could use an egg donor.
  • You might be able to have a special type of IVF that selects an embryo without ADPKD. This is called pre-implantation genetic testing (PGT).
  • You could have your developing baby (fetus) tested for ADPKD early in pregnancy. This is called chorionic villus sampling. You can choose whether to continue the pregnancy depending on the results.

Pre-implantation genetic testing

A few fertility clinics can offer people with ADPKD a special type of IVF called pre-implantation genetic testing (PGT).

For PGT, the clinic will test embryos made by IVF to find ones without ADPKD. An embryo without ADPKD is put in your womb. This means your baby won’t have ADPKD.

About a third of couples having PGT have a baby.

If you want to look into PGT, the first steps are:

  • Ask your GP whether PGT is available on the NHS in your area.
  • Ask your doctor to refer you to a genetics specialist to discuss PGT.
  • If the genetics service agrees you can have PGT, you’ll need to go to a specialist centre. There are not many in the UK so you may need to travel quite far.

To have PGT, the person with ADPKD will need genetic testing to find the gene causing their ADPKD.

Find out more about PGT on the Genetic Alliance website.

You may choose to have PGT privately if you can’t get NHS funding. Learn about choosing a clinic on the Human Fertilisation and Embryology Authority website.

Chorionic villus sampling

If you or your partner have ADPKD, you can have your developing baby (fetus) tested for ADPKD in the womb. This is called chorionic villus sampling. It’s done at weeks 11–14 of pregnancy.

To do the test, your pregnancy doctor will take a sample of cells from the placenta. This is usually done by putting a needle through your abdomen (tummy).

There’s a small risk of the test leading to miscarriage. This happens in fewer than 1 in every 200 women.

Doctors only recommend chorionic villus sampling when the results would help you decide whether to end a pregnancy. 

See the NHS website for more on:

Our helpline is available on 0300 111 1234, Facebook Messenger or email ([email protected]) for emotional support.

The charity Antenatal Results and Choices has a helpline for people considering the results of these tests. Call 0207 713 7486 or text 07908 683004.

How should we plan a pregnancy?

Here are 4 tips on planning a pregnancy.

1. Use contraception until the time is right

Use contraception until you’re ready to start trying for a baby. Your GP or kidney doctor can suggest suitable contraceptives for you.

They might suggest you use a contraceptive that doesn’t contain oestrogen. This depends on how ADPKD is affecting you. For example, your doctor may recommend you use contraceptives without oestrogen if you have liver cysts or if you have high blood pressure.

Emergency contraception (‘the morning after pill’) made with progesterone only is usually safe for women with kidney disease.2 Remember to let the pharmacist or GP know you have ADPKD.

2. Ask your GP or kidney doctor for advice

It’s useful to talk to your GP or kidney doctor before getting pregnant.

They can explain:

  • how ADPKD might affect your pregnancy
  • how having a baby might affect your kidneys
  • whether you need to change any medicines before or during pregnancy
  • the chance of your baby having ADPKD

They can also refer you to other experts for advice, such as:

  • a pregnancy doctor (obstetrician)
  • a specialist in genetics
  • a fertility specialist

They can make sure your kidney health and blood pressure are managed well, ready for pregnancy.3

If you’re on dialysis, your kidney doctor will explain any changes you might need to make.2

3. Take folic acid

All women trying to get pregnant (including those with ADPKD) should take folic acid Women usually take folic acid when trying to get pregnant and for the first 12 weeks of pregnancy.

Folic acid reduces the risk of problems with your baby’s spine and spinal cord.

4. Follow general advice on healthy living before pregnancy

Health advice for women trying to get pregnant includes:

  • stay a healthy weight
  • don’t smoke
  • don’t drink alcohol

You can learn more about trying to get pregnant on the NHS website.

What if we’re having trouble getting pregnant?

If you’re having trouble getting pregnant, speak to your GP. They’ll refer you to a fertility clinic or can provide treatment to help.

A doctor at a fertility clinic will explain:

  • the different fertility treatments available
  • the chance of success
  • any risks involved

One of the options might be in vitro fertilization (IVF).

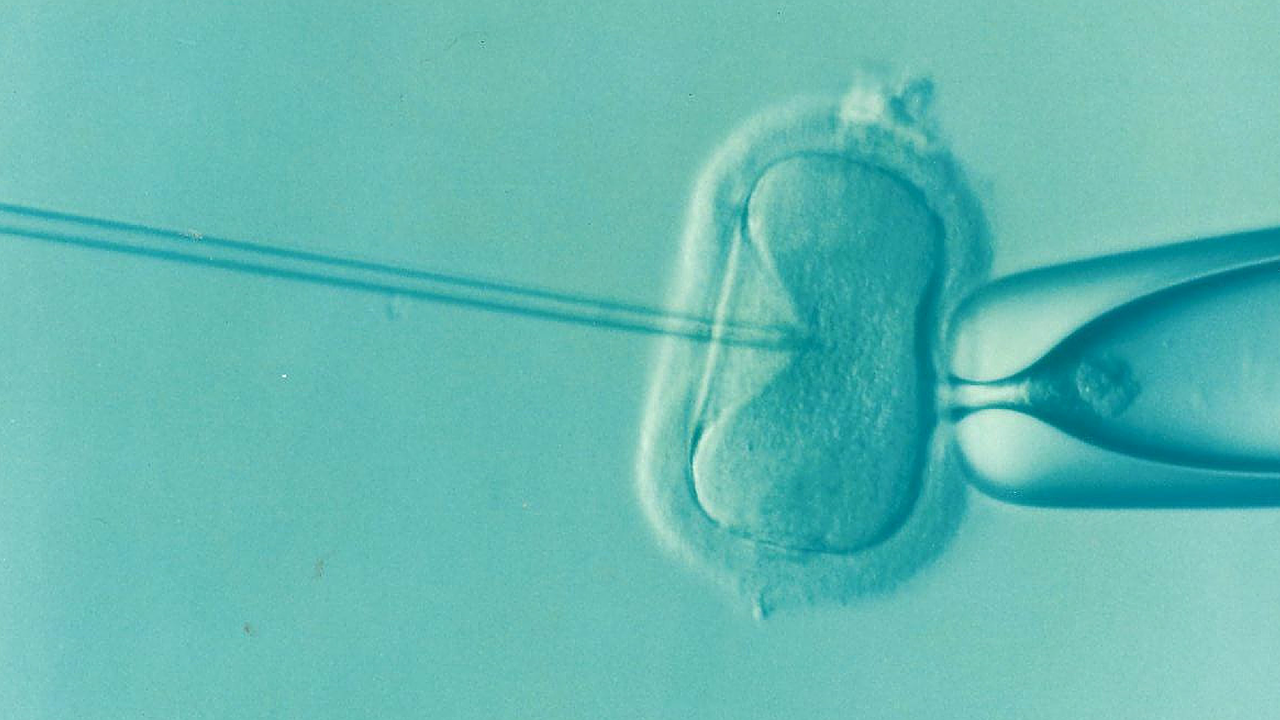
Image of an egg being injected with a sperm using a minute needle

Having IVF

If a fertility specialist thinks IVF may help you, a group of people (a local board) will decide whether the NHS will pay. Rules can differ by area of the UK.

The board’s decision may depend on:

  • your age
  • how long you’ve been trying to get pregnant
  • your weight
  • whether you smoke
  • whether you already have children
  • why your fertility is low

You can learn more about IVF on the NHS website.

You may choose to pay for IVF yourself if you can’t get NHS funding. Learn about choosing a clinic on the Human Fertilisation and Embryology Authority website.

Your fertility specialist may advise you against standard IVF if ADPKD is badly affecting your kidneys or liver. This is because the high doses of hormones used could make things worse. You might be able to have IVF without taking these hormones but it’s less likely to work.

Medicines in pregnancy

Which medicines can be a problem during pregnancy?

Some medicines are unsafe to use during pregnancy. They could harm your growing baby in the womb. We list some of these medicines in the table below.

Ask your doctor to review your medicines before you get pregnant. If you’re already pregnant, ask for a review right away.

Never stop taking medicines without talking to a doctor first. This could put you or your baby at risk.

You might need to swap to a different medicine, rather than stopping treatment. For example, women taking medicine for high blood pressure usually swap to a different medicine during pregnancy. This ensures that their blood pressure is still controlled, which is important for pregnancy.

Medicines that your doctor may advise you to stop or swap during pregnancy

Medicines to reduce cyst growth 

  • Tolvaptan (Jinarc®)

Medicines to control blood pressure

  • Angiotensin converting enzyme inhibitors (ACE inhibitors): captopril, enalapril, fosinopril, imidapril, lisinopril, moexipril, perindopril, quinapril, ramipril and trandolapril 
  • Angiotensin-II receptor blockers (ARBs): azilsartan, candesartan, eprosartan, irbesartan, losartan, olmesartan, telmisartan and valsartan  
  • Thiazide-like diuretics: chlortalidone, indapamide, metolazone and xipamide  

Medicines to treat overactive parathyroid glands 

  • Calcimimetics: cinacalcet and etelcalcetide

Medicines to treat high phosphate levels 

  • Non-calcium-based phosphate binders: sevelamer, lanthanum and sucroferric oxyhydroxide.

Antibiotics

·       Erythromycin and clarithromycin if you’re also taking the immunosuppressant tacrolimus or ciclosporin.

Immunosuppressants (used after kidney transplant)

  • Mycophenolate mofetil, methotrexate, cyclophosphamide, sirolimus and everolimus 
  • Rituximab (if a different medicine is suitable for you) 

Will being pregnant harm my kidneys?

Pregnancy can cause some damage to your kidneys. 

If your kidney function is medium (chronic kidney disease stage 3), having a baby could slightly affect your kidneys. The damage is about the same as ADPKD would usually cause over 2 years. 

If your kidney function is poor (chronic kidney disease stage 4 or 5), having a baby could affect your kidneys quite a bit. The damage is about the same as ADPKD would usually cause over 5 years. 

If you get high blood pressure during pregnancy, your kidneys are more likely to get some damage. 

Your kidney doctor can explain: 

  • how pregnancy might affect your kidney health 
  • how you can reduce risks 
  • signs of kidney problems to look out for 
  • treatments to help  

Will being pregnant harm my liver?

Many women with ADPKD have cysts in their liver. This is known as polycystic liver disease (PLD).  

Pregnancy can increase the growth of liver cysts. However, experts think pregnancy doesn’t increase your chance of having serious problems from PLD. There’s not been much research on this, so we can’t be sure.  

What about surrogacy or adoption?

If pregnancy is impossible or dangerous for you, surrogacy might be an option. This means another woman (the surrogate) carries your baby for you. Surrogacy is also an option for same-sex couples and people who are single.

The NHS does not fund surrogacy.

Find out about surrogacy on the Human Fertilisation & Embryology Authority website.

Another option for you may be adoption. As part of the approval process for adoption, the agency will assess your health. People with a long-term condition like ADPKD might be allowed to adopt.

The agency will explore with you:

  • whether your health might affect your ability to bring up children
  • the support you’ll have from your partner, close family and friends

Find out about adoption on the You Can Adopt website.

Where can I get practical and emotional support?

For information, practical advice and emotional support from people with experience of ADPKD, ring our confidential PKD Helpline 0300 111 1234. We’re open 9:30am to 5:00pm, Monday to Friday, except bank holidays.

You can connect with other people with ADPKD via our Facebook group or PKD support groups.

The charities Tommy’s and the National Childbirth Trust (NCT) also offer advice on pregnancy, birth, miscarriage, caring for babies, and more.

Will my ADPKD affect how well I can parent?

Having ADPKD won’t stop you being a good parent.

You might need more support with childcare if you’re unwell or having treatment. 

Ask your kidney doctor to explain how your ADPKD may affect your health as you get older.

Chat with your partner, family and friends about any worries. Having their support and putting plans in place can be reassuring.

You may find it helpful to talk to other parents with ADPKD. You can connect with them through our Facebook group or support groups.

More information from the PKD Charity

Useful information from others

Authors and contributors

Written by Hannah Bridges, independent medical writer, HB Health Comms Limited. Reviewed by Dr Mairéad Hamill, Nephrology Specialist Registrar, Kings College London, London, UK.

This page was adapted from an earlier version written by Dr Kate Bramham, Consultant Nephrologist and Olivia Snowball, Research Midwife.

With thanks to all the people affected by ADPKD who contributed to this publication.

Ref No: ADPKD.PLANPREG.V4.0
© PKD Charity 2026 (Charity No. 1160970)
First published: August 2026
Due to be medically reviewed: August 2029

Disclaimer: This information is primarily for people in the UK. We have made every effort to ensure that the information we provide is correct and up to date. However, it is not a substitute for professional medical advice or a medical examination. We do not promote or recommend any treatment. We do not accept liability for any errors or omissions. Medical information, the law and government regulations change rapidly, so always consult your GP, pharmacist or other medical professional if you have any concerns or before starting any new treatment.

If you don't have access to a printer and would like a printed version of this information sheet, or any other PKD Charity information, call the PKD Charity Helpline on 0300 111 1234 (weekdays, 9am–5pm) or email [email protected]

The PKD Charity Helpline offers confidential support and information to anyone affected by PKD, including family, friends, carers, newly diagnosed or those who have lived with the condition for many years.
Read more …Planning a pregnancy if you have ADPKD

Living well

Living well

Whether you’re newly diagnosed or have been living with ADPKD (autosomal dominant polycystic kidney disease) for some time, having ADPKD is likely to affect you emotionally at times.

This web page brings together advice from other people with PKD and experts. We hope it helps you to find practical ways to live well with ADPKD and to feel freer and positive about the future.

Contents

Three ways to lighten the load of PKD

Polycystic kidney disease (PKD) is lifelong but it needn’t be life defining. Different people with PKD face different challenges and cope in different ways. Finding practical and emotional ways of coping that work for you can help you regain control of your life.

We asked 12 people affected by PKD to share the ways in which they cope. Some have PKD personally, while others care for a partner or family member with PKD. Each person coped differently, but three themes were common:

1. Be informed

Knowledge is power! Many people with PKD tell us that knowing more about the disease has helped them to feel in control. Being clued up can help you to look after your kidneys and protect your physical and mental health. You could research the best lifestyle and diet for you or the treatments and care to which you’re entitled, for example.

“Read up on the disease. Basically, stay well informed.
I found it took away a lot of the worry.” Julie

Get in the habit of asking questions of your GP, your kidney specialist and those with first-hand experience. You can find information on our website or through our educational events or PKD helpline (0300 111 1234; open Mon to Fri 9.30 am to 5.00 pm, except bank holidays).

2. Talk to others

You may feel that others don’t understand your PKD. Sometimes, friends, family, colleagues and healthcare professionals may struggle to grasp how it affects you.

However, you’re not alone! Others with PKD may well have faced challenges similar to yours. They can listen and understand.

You can connect with people through our support groups, Facebook groups or PKD helpline (0300 111 1234; open Mon to Fri 9.30 am to 5.00 pm, except bank holidays).

Be open and honest with friends and family too, so they know how to help.

 “Join the Facebook group to hear the views and support from those who are experiencing or have experienced what you’re going through — who 'get it' when it comes to PKD.” Andy

3. Own your life

A philosophy of living life to the full — and not letting PKD rule your life — is shared among many people with PKD. This can be hard to do at times, but the mental shift can have a big positive effect. For some, it means taking each day as it comes. For others, it means staying active or not setting limits on what they can and can’t do.

Not letting PKD define your life is about staying positive and learning to adapt, but it’s not about powering on regardless. To stay strong emotionally and physically, accept when you need to recharge.

“Don’t let PKD interfere with life until it has to.” Melanie

See below for advice on positive thinking and being mentally resilient.

Expert online advice on coping

Although PKD brings unique experiences and challenges, coping strategies that can help are quite universal. Here is a collection of useful websites and resources on coping from other organizations. Some of these organizations specialize in kidney disease, while others have a broader focus.

Emotional Resilience. By Kidney Care UK and the Renal Association (UK)
Leaflet (PDF)
Introduces emotional resilience. It provides tips on how emotional resilience can help you to cope with stresses in your life.

Coping with Physical Illness. By the Royal College of Psychiatrists (UK)
Website  │  Video
Information to help you identify when you’re anxious or depressed. It covers when to seek help, treatments available, how to help yourself, and how friends and family can help too.

Dealing with anxiety. By the PKD Charity (UK)
Newsletter article (PDF)
How to recognize, accept and lessen feelings of anxiety.

Relaxation. By MIND (UK)
Website  │  Booklet (PDF)
8 ways to relax.

Mindfulness. By MIND (UK)
Website  │  Booklet (PDF)
Introduces mindfulness: a technique to help you feel more self-assured, calm, and able to cope. It gives exercises you can try right away and explains how you can learn mindfulness.

Positive Thinking. By The Mayo Clinic (USA)
Website
A good starting point for people interested in positive thinking. It describes positive and negative thinking and explains how you can practice overcoming negative thoughts.

Talking Therapies and Counselling. By MIND (UK)
Website
Explains what talking therapies are, what happens during therapy, how to get the most out of therapy, and where to find a therapist.

Cognitive Behavioural Therapy (CBT). By MIND (UK)
Website │  Booklet (PDF)
Explains the theory behind CBT, the conditions it can help to treat (including pain, anxiety and depression), what happens in CBT sessions, and how to find a therapist.

What challenges do people with PKD face?

People with PKD and those caring for them can face a range of challenges. Each person’s experience is unique and will change over time.

Here are aspects of PKD that 12 people with PKD told us can be challenging:

  • receiving a diagnosis
  • concerns about future health
  • not knowing when kidney function will worsen
  • financial concerns
  • others’ lack of knowledge and understanding
  • effect on day-to-day life
  • following a special diet
  • dialysis or a transplant
  • lack of support.

What emotions can PKD cause?

Receiving a diagnosis of PKD personally or hearing of a loved one’s diagnosis can be a very emotional time. Many people describe it as a time of crisis, although others feel numb at first.

Although people with PKD adjust over time, the ongoing challenges of living with the disease can sometimes cause intense emotions, stress, anxiety and depression. Some people with ADPKD describe it as an emotional roller coaster.

There may be particular periods when it becomes harder to cope, such as when waiting for a transplant. As your kidney function decreases, imbalances of chemicals in your blood and the side effects of medications can alter your emotions too.

Challenging emotions

Everybody is different. Below are some feelings that you may experience after a PKD diagnosis and at periods in your life. These are all emotions that people with or without PKD are likely to feel in their life. However, living with a long-term condition can make these emotions more frequent, intense or sudden.

Distress

Confusion

Loneliness

Anxiety

Shock

Denial

Disbelief

Anger

Frustration

Guilt

Resentment

Sadness or depression

Fear

Helplessness

Loss of confidence

Altered self-image

Grief


Exploring your emotions

Emotions are not random. They can remind us what really matters to us, although we don’t get to choose when they show up.

While we may crave moments of happiness and calm, being willing to experience (rather than ignore) more challenging emotions is important too. Being curious and kind in acknowledging your own emotions can help you to control their intensity and decide how to respond positively.  

Ask yourself what you’re feeling and why. This might take some time and space to do. Your emotions may show up in your body too, for example as tension.

To learn more about how to spot your emotions and process them, see Expert online advice on coping above.

Signs of stress

Living with PKD can cause emotional stress.

Recognizing the signs means you can be kind to yourself and get the practical and emotional support you need. Signs include:

  • feeling irritable, sad or guilty
  • problems concentrating or making decisions
  • increased or decreased weight or appetite
  • altered sleep patterns or difficulty switching off
  • loss of interest or enjoyment in hobbies or socializing
  • negative thinking.

Finding support

For different ways to get emotional and practical support, see the support area of our website.

There are many ways to connect, including support groups, Facebook groups, and via our helpline 0300 111 1234 (open Mon to Fri 9.30 am to 5.00 pm, except bank holidays).

Authors and contributors

Written by Hannah Bridges, independent medical writer, HB Health Comms using the views and feedback of people with ADPKD.

With thanks to all those affected by ADPKD who contributed to this publication.

Ref No. ADPKD.LW.V2.0 last updated June 2023 next review June 2026

Disclaimer:  This information is primarily for people in the UK. We have made every effort to ensure that the information we provide is correct and up to date. However, it is not a substitute for professional medical advice or a medical examination. We do not promote or recommend any treatment. We do not accept liability for any errors or omissions. Medical information, the law and government regulations change rapidly, so always consult your GP, pharmacist or other medical professional if you have any concerns or before starting any new treatment.

We welcome feedback on all our health information. If you would like to give feedback about this information, please email [email protected]

If you don't have access to a printer and would like a printed version of this information sheet, or any other PKD Charity information, call the PKD Charity Helpline on 0300 111 1234 (weekdays, 9am-5pm) or email [email protected]

The PKD Charity Helpline offers confidential support and information to anyone affected by PKD, including family, friends, carers, newly diagnosed or those who have lived with the condition for many years.

Read more …Living well

Diet and lifestyle in ADPKD

Diet and lifestyle in ADPKD

This factsheet is for people living with autosomal dominant polycystic kidney disease (ADPKD) who have normal to moderately reduced kidney function (chronic kidney disease stage 1, 2 or 3), their family and friends. It gives information and tips on a diet and lifestyle that can help to keep you healthier if you have ADPKD.

Your own diet and lifestyle needs might differ from those given in this factsheet. The advice we give might not be right for you if:

  • you have severely reduced kidney function or kidney failure (chronic kidney disease stage 4 or 5)
  • you’re on dialysis 
  • you’ve had a kidney transplant.

Always seek the personalized advice of a kidney specialist before making any changes to your own or your child’s diet or exercise plans.

Contents

Six tips to protect your health

No diet or lifestyle measures have been shown to prevent cysts developing in people with autosomal dominant polycystic kidney disease (ADPKD). However, a healthy lifestyle may: 

  • help to protect your kidney function
  • reduce your blood pressure
  • lower your risk of heart and blood vessel problems (cardiovascular disease), such as stroke. 

Keeping your blood pressure down is especially important because high blood pressure can damage your kidneys if you have ADPKD.  

Tips for a healthy diet and lifestyle include: 

  1. Stay a healthy weight
  2. Drink enough fluid to stay hydrated
  3. Have a healthy diet that is low in salt
  4. Drink alcohol in moderation only
  5. Exercise regularly
  6. Stop smoking

We explain these below. 

1. Stay a healthy weight

If you have early ADPKD, being a healthy weight can help to reduce the speed at which your kidney disease worsens. For everyone, being a healthy weight can reduce your risk of high blood pressure and cardiovascular problems.

While it can affect your health to be overweight, being underweight can make you unwell too. This is because your body isn’t getting the nutrients it needs.

Your doctor can advise you on the weight that is healthy for you. A common way of checking your weight is to calculate your body mass index (BMI) and compare this to the healthy range. To calculate your BMI, you’ll need to know your height and weight. The NHS website has a simple, online BMI calculator.

A healthy BMI is between about 18.5 and 24.9 kg/m2 for most people. Being over 24.9 kg/m2 usually means you’re overweight, while being less than 18.5 kg/m2 means you’re underweight.

Check with your doctor if:

  • your kidneys or liver are larger than normal ­— you may need to take this into account when working out your healthy weight
  • you’re of South Asian, Black or minority ethnic origin, as your ideal BMI may be slightly lower than the range given above.

If you want to lose weight, see the NHS website for how to make a weight-loss plan and for advice. Also talk to your doctor about a referral to a dietitian for advice and support. You can also ask for a referral to a dietitian if you’re underweight.

2. Drink enough fluid to stay hydrated

It is not proven that drinking extra fluid can be helpful if you have ADPKD. No studies have shown that drinking extra fluid slows the growth of kidney cysts.

Expert recommendation for people with ADPKD 

Kidney experts recommend that you drink enough so you don’t get thirsty, but don’t drink excessively.

In the UK climate, drinking about 6-8 glasses (about 1.2 litres) of water or other liquids each day should be about right to keep you hydrated. This guidance is for everyone, not just people with ADPKD. If you’ve lost more fluid through sweating or diarrhoea, you may need to drink more.

Be careful not to have a lot of sugary drinks. These can cause tooth decay and have many calories.

There is nothing to suggest that people with ADPKD shouldn’t drink caffeine. Some researchers have a theory that caffeine could affect cyst growth, but this hasn’t been proven. Drinking a low amount of caffeine each day doesn’t affect cardiovascular health. While it seems sensible to avoid lots of caffeine, drinking up to 2 cups of coffee or 4 cups of tea a day is thought to be okay.

How do you know if you’re drinking enough water to stay hydrated? The urine colour chart below will give you an idea.

Checking the colour of your urine

This urine chart is a rough guide only. It doesn't apply to people who have been given specific medical advice about how much fluid to drink. Computer screens and printers can make colours appear different. If you have any concerns about your urine colour, please speak to your doctor.

3. Have a healthy diet

There is no recommended special diet that people with ADPKD should follow. But, a healthy diet can help control your weight, which helps to reduce your blood pressure and risk of cardiovascular disease.

For a healthy balanced diet:

  • eat 5 portions of fruit or vegetables a day
  • base your meals on starchy foods, such as potatoes, bread, rice or pasta
  • eat some dairy (or dairy alternatives, such as soya drinks)
  • have protein, such as beans, pulses, fish, eggs, or meat
  • only have small amounts of food high in salt, sugar, and fat, and choose unsaturated fats
  • choose unsaturated oils and spreads and eat these in small amounts.
  • use fresh ingredients to limit the amount of processed and ready-made food you eat.

You’ll find more advice about healthy eating at the NHS Live Well and the British Nutrition Foundation websites.

Do you have a health condition in addition to ADPKD that requires you to avoid certain foods? Talk to your doctor about how you can best manage the dietary requirements of your different conditions. You can ask them for a referral to a dietitian if you need more advice and support on this.

Eat less salt

Salt is made up of sodium and chloride. Pure sodium can also be found in some foods. Keeping salt (and sodium) intake down can be good if you have ADPKD. This is because too much salt can speed up ADPKD progression and increase your blood pressure.

In a study of people with ADPKD, those who ate more salt than recommended had a faster decline in kidney function than those who stuck to recommendations. Those eating more salt also had bigger increases in kidney size over time.

Salt can be used as an ingredient in many foods, including bread, breakfast cereals, bacon, ham, sausages, takeaways and ready meals. It’s sometimes listed in ingredients as sodium.

Expert recommendations for people with ADPKD

If you’re an adult, aim to keep your daily salt intake to no more than 5g, preferably less. This is just under a teaspoon of salt, which is the same amount of sodium as 2g of pure sodium. This includes salt added at the table or during cooking, as well as ‘hidden’ salt in food.

Children under 11 and babies should eat less salt than adults.

The recommended maximum amount of salt that children and babies should eat per day depends on age:

  • 1-3 years old — no more than 2g salt a day (0.8g sodium)
  • 4-6 years old — no more than 3g salt a day (1.2g sodium)
  • 7 and older — no more than 5g salt a day (2g sodium).

Especially, if you eat a lot of processed or ready-made food, keeping your salt intake down takes dedication. Check food labels carefully for the amount of salt (sodium).

Some packages use colour coding

  • Red= high salt (more than 1.5g salt per 100g)    
  • Amber = medium salt (between 0.3g and 1.5g of salt per 100g)
  • Green = low salt (0.3g salt or less per 100g)

Some manufacturers show salt content by portion size, while others show it per 100g or 100ml. Either way, remember to take into account how much of the food you’re eating when calculating your salt intake.

If the label shows the amount of sodium, you’ll need to multiply this figure by 2.5 to find out how much salt the food contains.

In "low salt" or "low sodium" products, manufacturers may have replaced some of the sodium with potassium. This can be a problem for a very small number of people with ADPKD. Ask your kidney specialist whether you need to limit the potassium in your diet. Don’t avoid potassium unless they tell you to, because your body may miss out on some of the nutrients it needs. 

If you’re interested in campaigning for less salty foods at your local restaurants or shops, see the Action on Salt website.

Eat a moderate amount of protein

Protein provides energy. It’s needed for growth and to maintain good health. Foods rich in protein include meat, fish, eggs, dairy, soya products, nuts and pulses.

A recent study of people with ADPKD found no link between the amount of protein they ate and kidney function or size. There is little proof to suggest otherwise.

The amount of protein you need depends on your age and body size. Eating very little protein might stop your body getting all the nutrition it need. However, eating very high amounts of protein might not be good for your kidneys. This has been shown in the general population but not in people with ADPKD.

Expert recommendations for people with ADPKD

Adults with ADPKD without severely decreased kidney function should eat a moderate amount of protein. This is about 0.8-1.0 g of protein for each kg of your body weight each day. For example, if you weigh 65kg you should eat about 52-65g of protein each day.

Ask your doctor for advice if your kidney function is severely decreased. This would be chronic kidney disease stage 4 or 5 or an estimated glomerular filtration rate (eGFR) below 30 ml/min/1.73 m2.

Table: Protein content of common foods

Animal - protein per 100g Protein per portion
Cooked red meat or chicken breast - 29-32g

38—40g in half a hand size piece

Cooked fish - 20-25g

30g in a half a hand size piece

Cow's milk – 3.4g

4.4g in half a glass (125mg)

Cheddar cheese - 25g

7.6g in a piece the size of 2 thumbs

Plain yoghurt - 5-6g

5.8g in 4 tablespoons

Eggs - 14g

5g in 1 egg

Vegetable - protein per 100g Protein per portion
Cooked pulses (eg beans/lentils) - 5-8g

About 10g in 6 tablespoons

Tofu - 8g

8g in a 100g slice

Nuts - 14-20g

About 4.1g in 2 tablespoons

Eat less processed food

Highly processed foods (sometimes called ‘ultraprocessed’ foods) might increase risks of kidney disease. This has been shown in the general population, but not in people with ADPKD.

Highly processed foods tend to contain a lot of salt, sugar and additives. Examples are some sausages and ham, ice cream, crisps, pizza, breakfast cereals, carbonated drinks, and biscuits.

Instead, make meals from fresh ingredients when you can. A way to do this is to eat a plant-based diet.

If you follow a plant-based diet, you’ll eat mainly vegetables, fruits, nuts, seeds, wholegrains, beans, pulses and lentils. You’ll have few or no animal products (meat, milk, cheese or eggs). Kidney Care UK has information on plant-based diets for people with chronic kidney disease.

What about fasting, low-carb diets, or keto diets?

There’s no proof that restricting the number of calories you eat, restricting when you eat, or following a low-carbohydrate diet can slow ADPKD progression. Some of these eating plans are called ‘keto diets’ or ‘ketogenic diets’.

The evidence so far on keto diets is mainly from studies of mice and rats. A large well-controlled trial has not been done in humans yet, but some trials are underway.

We will update our blog on keto diets as results come out.

 The PKD Charity’s view

We do not recommend a keto diet for people with ADPKD. This is because we can’t be sure there are any benefits or that these would outweigh the risks.

We recommend you speak to your kidney specialist, doctor, or a dietitian specializing in kidney disease before trialling any diets that differ to a normal healthy diet.

Help selecting healthy foods

The best way to select healthy foods is to choose fresh food. This has little processing or additives.

Modern lifestyles mean many of us eat some processed food, even if it’s only a small amount. Some products are surprisingly high in salt, added sugar, saturated fats and calories. Apps are available to help you select healthy food. Also, many products have the traffic light system on them.

With the free NHS Food Scanner app you can scan barcodes on foods, to see what’s in the product and get suggestions for simple, healthier switches. 

Many food packages — especially supermarket brands — now have a colour-coded summary on the front. This helps you to tell whether the food is high in fat, saturated fat, sugar and salt:

  • red = high
  • amber = medium
  • green = low.

The more green on your food labels, the better!

4. Drink alcohol in moderation only

Your liver is the main organ that breaks down alcohol in your body. Unless you prefer to do so, there’s no need to avoid alcohol completely if you have ADPKD and are otherwise healthy. But alcohol does increase people’s risk of accidents and diseases including cancer, stroke, heart disease and liver disease.

Expert recommendations for all people

For lower risk drinking:

  • Drink no more than 14 units a week regularly (whether you’re a man or a woman).
  • Don’t drink any alcohol on 2—3 days of the week.
  • Spread your drinking out over the week, rather than drinking a lot of alcohol in one session.

Drink Aware website has lots of information on reducing your alcohol intake. It also explains the amount of alcohol in common drinks and the effects of alcohol.

5. Exercise regularly

Regular exercise is an important part of a healthy lifestyle because it helps to control your weight and blood pressure. Reducing your blood pressure means you’re less likely to have cardiovascular disease. Healthy blood pressure can also help to protect your kidneys from damage.

There are no special guidelines for people with ADPKD on the minimum amount of exercise to do.

Expert recommendations for all people

  • If you’re 19–64 years old aim for 2.5 hours of moderate or vigorous physical activity a week
  • Children and young people (5–18 year olds) should aim for at least 60 minutes of moderate to vigorous physical activity every day
  • Whatever your age, try not to spend long periods of time sitting or lying down

Moderate physical activity is enough to get you slightly out of breath, raise your heart rate, and make you warmer. You can split your exercise into sessions of 10 minutes or more throughout the week. So for example, you could do 5 exercise sessions of 30 minutes on 5 days of the week.

Suggestions include:

  • Brisk walking
  • Swimming
  • Dancing
  • Cycling
  • Vigorous gardening and housework

Simple changes can add up. Choosing to walk or cycle part of the way to work or choosing the stairs instead of the lift could help you to keep fit.

If you have enlarged kidneys, there’s a risk you could damage a kidney by taking part in riskier sports (for example horse riding) or contact sport (for example rugby, hockey, or martial arts). If you do damage your kidneys playing sport, it could cause a burst cyst, bleeding and pain.

It’s your choice which sports you do, but consider your doctor’s advice, especially if your kidneys are very large.

People with ADPKD can be at higher risk of having an aneurysm (a ballooning of a blood vessel). If you have an aneurysm and are unsure whether this affects the physical activity you can do, ask your doctor for advice.

For ideas of activities and tips on how to stay active, see the NHS website.

6. Stop smoking

Smoking is bad for anyone, but it’s especially important to avoid smoking if you have any type of kidney disease. Smoking can increase the speed at which your ADPKD progresses and lead to kidney damage. Smoking is also a known cause of cardiovascular disease.

It’s never too late to stop smoking, but it can be difficult if you have been smoking for many years. You can find ways to quit at Smokefree. Or ask your doctor to refer you for free, expert support from your local NHS Stop Smoking Service.

More information from the PKD Charity:

Information and support from others:

Authors and contributors

Authors and Reviewers: Dr Hannah Bridges, Independent medical writer; Helen Botham, Salford Royal NHS Foundation Trust for the first version; Jane Richardson, Renal Dietitian, Manchester Foundation Trust for this version.

With thanks to all those affected by ADPKD who contributed to this publication.

Ref No: ADPKD.DL.V3.0
Last updated: June 2023
Next scheduled review: June 2026

Disclaimer:  This information is primarily for people in the UK. We have made every effort to ensure that the information we provide is correct and up to date. However, it is not a substitute for professional medical advice or a medical examination. We do not promote or recommend any treatment. We do not accept liability for any errors or omissions. Medical information, the law and government regulations change rapidly, so always consult your GP, pharmacist or other medical professional if you have any concerns or before starting any new treatment.

We welcome feedback on all our health information. If you would like to give feedback about this information, please email [email protected]

If you don't have access to a printer and would like a printed version of this information sheet, or any other PKD Charity information, call the PKD Charity Helpline on 0300 111 1234 (weekdays, 9am-5pm) or email [email protected]

The PKD Charity Helpline offers confidential support and information to anyone affected by PKD, including family, friends, carers, newly diagnosed or those who have lived with the condition for many years.

Read more …Diet and lifestyle in ADPKD

Talking to your child about ADPKD

Talking to your child about ADPKD

This information is for parents, guardians and carers. It gives tips on talking to children and young people if they or another family member has autosomal dominant polycystic kidney disease (ADPKD). We include suggestions for how to explain the condition and its treatment. 

If you’re looking for information on symptoms and testing in children, we have a separate web page on this topic.

Contents

Why talking helps

If your child has ADPKD, you may find it difficult to know what information to give them, especially if you feel it worries them. Likewise, if you or another family member has ADPKD, talking to your child (or children) about the condition might be stressful.

Children usually want information first from their parents or guardians.

A picture of a group of children.

Conversations can help children and young people to:

  • cope and feel less confused
  • feel valued and respected
  • get accurate information
  • feel able to ask questions
  • be confident talking with others

Talking with children as they grow up allows them to gradually understand ADPKD and what it means for them and their family. In general, children cope well with new information and don’t dwell on the risk of disease. They’re focussed on living their lives, friendships, school and personal interests.

Finding out about ADPKD later can be more of a shock. Young people may ask difficult questions but not be emotionally prepared for the answers.

If you want to talk with your child about ADPKD, the tips below may help you prepare.

Starting a conversation

  • Look for natural opportunities to talk, for example after a TV programme or school lesson about health or kidneys.
  • Watch out for changes in behaviour that might suggest your child is worried about something they have seen or heard. It might be time to talk.
  • Prompt your child to ask questions. By age 8, children may hold back from asking questions for fear of upsetting their parents. Let them know it’s okay to ask.
  • Keep it informal. Children and young people often prefer to chat while in the car or cooking, for example.
  • Prepare emotionally. Talking about ADPKD can be hard on adults. Choose a time when you’re ready and calm.

Having a good conversation

  • Check you understand what your child is asking.
  • Use simple words they can understand.
  • Provide small amounts of information at a time.
  • Be ready to explain things several times. Children might not understand first time round. Like adults, they need time to digest information.
  • Give the condition a name: ADPKD, PKD, or kidney cysts. This reduces fear and gives control.
  • Talk about emotions. Reassure your child that they’re not alone in how they feel. Share how you’re feeling too.
  • Listen.
  • Don’t avoid answering a question. Children like trust and honesty.
  • Check that you’ve answered your child’s questions. If you cannot answer, explain why. Give the answer later if you can.

After the conversation

  • Your child might need time. After getting new information, their schoolwork may be affected for a short time.
  • Encourage future chats. Just like adults, children take time to process information and may have questions later.
  • Be prepared for future questions. If these come up at tricky moments, agree a good time to chat later.

Suggested topics and wording by age

There is no ‘right age’ to talk. Children learn at different speeds. You can begin to talk about ADPKD from when your child is 2 years old. Below we give some suggestions about suitable topics and phrases by age group.

Choose words to suit your child’s age. For example, ‘PKD’ is an easier term for younger children to remember, whereas older children might want to get used to the full term ‘ADPKD’.

You’ll need to address issues specific to your family as they arise. For example, if a family member is soon to have a kidney transplant, you could explain why it’s needed, recovery times, and any changes to childcare.

Aged 7 or younger

Children this age often understand short-term illnesses (for example, having a cold).

You could talk about:

  • What kidneys are: “You have two kidneys inside you. Each is the size of your closed hand. They clean your blood and make pee with the water you don’t need.”
  • Having a kidney condition: “My kidneys are poorly.”
  • Trips to hospital: “I need to go to the hospital sometimes so doctors can help my kidneys feel a bit better.”
  • Reassurance: “It’s not your fault that I’m sad today.”

Age 8 to 11

Children this age often understand longer term illness and the idea that you can inherit features from a parent.

You could talk about:

  • What PKD is: “I have a kidney problem. My kidneys have lots of balls of fluid in them called cysts. This means my kidneys don’t work as well as usual. I was born with this problem. It’s called PKD.”
  • Genes control how your body is made and how it grows. Sometimes the genes for kidneys can cause cysts to grow. These cysts can stop the kidneys from working well.
  • How PKD is inherited: “I have PKD because I inherited a gene that causes the condition from grandpa.”

Age 12 to 14

Children this age often understand genes and inheritance.

You could talk about:

  • The chance of your child having ADPKD: “Because I have ADPKD, there’s a chance you could have it too.”
  • Why one child has ADPKD and the other doesn’t: “You and your brother/sister have many different genes. You have PKD because you inherited a gene that causes the condition from me/your mum/your dad. Your brother/sister doesn’t have the same gene.”
  • The age that ADPKD causes symptoms: “Most people with ADPKD are about 30 or 40 years old when their kidneys stop working so well. The age at which problems begin differs between people.”
  • Having checkups: “I go to hospital once a year to check how well my kidneys are working.”
  • Treatments: “No treatments can cure ADPKD. Lots of treatments can help with the problems it causes though. For example, when I had a kidney infection, I took antibiotics and that got rid of the infection.”

Age 15 to 17

Children this age often understand how inherited conditions might affect them and their future children.

You could talk about:

  • The chance your child has ADPKD: “Because I have ADPKD, there’s a chance you have it too. It’s a 1 in 2 chance (50%).”
  • Why one child has ADPKD and the other doesn’t: “About half of your genes are different to your brother’s/sister’s. You inherited a gene that causes ADPKD from me/your mum/your dad. Your brother/sister doesn’t have ADPKD because they inherited a different gene from me/your mum/your dad.”
  • Tests for ADPKD: “You could be tested to see if you have ADPKD. A doctor could check your kidneys using a scan or could do a blood test to look for the PKD gene.”
  • Deciding whether to be tested: “Would you like to know whether you have ADPKD? You can talk to me or a specialist about the good and bad sides to testing whenever you feel ready.”
  • Check-ups: “If you have ADPKD, you probably won’t get any problems until you’re much older. Every year or two, doctors can do simple tests to check your kidneys are doing ok.”

Videos to show your child

Videos are a great way to help children take in new information in a relaxed way.

Check any video before playing it to your child:

  • Is it aimed at their age group?
  • Is the topic right?
  • Does the information seem accurate?
  • Is anything shown or said that could cause worry?

Here are some suggestions of videos that introduce how the kidneys work:

Getting support and advice

You may find it helpful to talk to other family members, friends and health professionals about how to talk with children about health problems. Chatting to other parents through our face-to-face and online support groups and Facebook groups might be useful too.

You may want to chat to the school at times you think your child could be worried about their own or a relative’s health. This means teachers can be mindful and ready to give support.

The Genetic Alliance UK also has a team to answer questions about inherited conditions. Call 0300 124 0441 or email [email protected] to get in touch.

More from the PKD Charity

Information and support from others

Authors and contributors

Original version by Alison Metcalfe, Professor of Health Care Research & Dean for Research, King’s College London, and Gill Plumridge, University of Birmingham. Edited and updated in 2025 by Hannah Bridges, PhD, Independent Medical Writer and HB Health Comms Limited, UK.

With thanks to all those affected by ADPKD who contributed to this publication.

Ref No: ADPKD.TAATC.V2.0

© May 2025.

Latest version: May 2025.

Due for medical review: May 2028.

Disclaimer: This information is primarily for people in the UK. We have made every effort to ensure that the information we provide is correct and up to date. However, it is not a substitute for professional medical advice or a medical examination. We do not promote or recommend any treatment. We do not accept liability for any errors or omissions. Medical information, the law and government regulations change rapidly, so always consult your GP, pharmacist or other medical professional if you have any concerns or before starting any new treatment.

If you don't have access to a printer and would like a printed version of this information sheet, or any other PKD Charity information, call the PKD Charity Helpline on 0300 111 1234 (weekdays, 9am–5pm) or email [email protected]

The PKD Charity Helpline offers confidential support and information to anyone affected by PKD, including family, friends, carers, newly diagnosed or those who have lived with the condition for many years.

Read more …Talking to your child about ADPKD

Symptoms and testing in children

Symptoms of ADPKD and tests in children

This information is for parents who have been told that their child might have autosomal dominant polycystic kidney disease (ADPKD). It’s also for parents of children already diagnosed with ADPKD. Most older teenagers will be able to follow this information too. It explains how ADPKD can affect children, the tests available to diagnose ADPKD, and what happens next.

Contents

Key facts

  • ADPKD is a rare condition causing many fluid-filled pouches (cysts) to grow in the kidneys.
  • Most children with ADPKD don’t have symptoms that cause problems.
  • Up to a quarter of children get symptoms such as weeing often, high blood pressure, pain or urinary tract infections.
  • Children with a close relative who has ADPKD can usually have a kidney scan or blood test to check for ADPKD.
  • Your doctor can put you in touch with a kidney specialist and specialist in inherited conditions to help you decide whether to get your child tested.
  • Children with ADPKD usually have check-ups on their kidneys and blood pressure once every 2 years.
  • Most children with ADPKD don’t need treatment until they reach adulthood.
  • If your child has high blood pressure, medicines can help to lower it.
  • A healthy diet and lifestyle are good for all children, whether or not they have ADPKD.
  • Always check with your doctor or pharmacist that any medicine is safe for your child before giving it to them.

What is ADPKD?

About 1 in every 1,000 to 2,500 people are born with ADPKD. The condition causes many fluid-filled pouches (cysts) to grow in the kidneys. These cysts form in the fine tubes that filter blood to make urine. As the cysts become larger, the kidneys grow in size and stop working properly.

A picture of a normal kidney compared with an ADPKD kidney. The ADPKD kidney is much larger and has many cysts of varying size.

ADPKD is a ‘progressive’ condition, meaning it gets worse over time. It usually takes decades for the cysts to grow as much as those shown in the drawing.

Symptoms of ADPKD in children

Often, ADPKD doesn’t cause problems until adulthood.

Kidney cysts can start forming in childhood, but children usually have plenty of normal kidney tissue to filter their blood.

Most children with ADPKD don’t have symptoms that cause problems. However, up to a quarter of children with ADPKD have some symptoms or problems related to ADPKD. These can include:

A picture of the symptoms of ADPKD in children, as listed in the text above.

About 1 in every 5 children with ADPKD has high blood pressure. This usually doesn’t cause symptoms but can be picked up using a blood pressure monitor. High blood pressure is often the first sign of ADPKD (although many people don’t get it until adulthood).

When you have high blood pressure, it means your blood is being pumped around your body with more force. It’s important that blood pressure is checked in people with ADPKD and treated if it becomes too high. We explain this later. 

Children are more likely to get symptoms as their ADPKD gets worse and their cysts become bigger.

Can children be tested for ADPKD?

Tests are available to check for ADPKD in children and adults. If a child’s biological mum or dad has ADPKD, there is a 1 in 2 (50%) chance that the child has ADPKD too. By ‘biological’, we mean parents by birth, not by fostering or adoption.

Children with a biological parent or other close relative with ADPKD can have a test for ADPKD if their parents and doctor agree. Children who are old enough to understand should help to decide.

Children who don’t have a close relative with ADPKD can’t normally have a test for ADPKD. This is because the condition is so uncommon. However, if a doctor notices a possible sign of ADPKD (for example, kidney cysts on a scan done for other reasons), then the child may be offered an ADPKD test.

If you (or your child’s other parent) have ADPKD and you’d like to look into getting your child tested, speak to your doctor. They can refer you to a kidney specialist and a specialist in inherited conditions to help you decide.

How are tests for ADPKD done?

There are two tests that can be used to diagnose ADPKD:

  • an ultrasound scan
  • a test to look for ADPKD genes

Children with a close relative with ADPKD can have either test. Children without a relative with ADPKD but with a possible sign of ADPKD usually have a gene test.

Ultrasound

A radiologist can use an ultrasound machine, which uses sound waves, to see inside the body.

A radiologist sits on a chair with an ultrasound machine and screen in front of them. A person lies on a bed next to the radiologist, ready for their scan.

Using ultrasound they can check for kidney cysts in children. It takes 15–45 minutes, is painless, and the sound waves don’t cause harm.

If your child has a close relative with ADPKD and more than one cyst is seen on their ultrasound scan, it’s very likely that they have ADPKD. To confirm this for sure, they’ll need either another scan when they’re older or a genetic test.

If cysts are not seen, this could mean either:

  • your child does not have ADPKD
  • your child has ADPKD but their cysts are too tiny to see on a scan

In this case, your doctor will suggest another scan when your child is 15–18 years old or an adult. Your child can decide if and when to have this future scan.

Tests for ADPKD genes

ADPKD is caused by an altered gene. Genes are instructions in the cells of our bodies and tell the body how to grow and function. People with ADPKD usually have an alteration (a mutation) in a gene called PKD1 or PKD2. Uncommonly, a different gene is involved. The altered gene causes some changes to a person’s kidneys, which is why the cysts grow.

A person can be tested to see whether they have a faulty PKD gene. These tests for are usually done on a small sample of blood.

A laboratory worker checks the DNA in the blood cells for a faulty PKD gene. If they look for a single gene (or only a few genes), this is called a genetic test. If they read the whole genetic code, this is called genomics. Either test can be used to diagnose ADPKD.

If the precise gene alteration causing ADPKD in other family members is already known, a genetic or genomic test can say for sure whether or not your child has ADPKD.

For more information on the genetics of ADPKD and these tests, see our factsheet Genetic testing and counselling for ADPKD.

Deciding whether to go ahead with an ADPKD test

When a parent has ADPKD, they often ask us whether or not they should get their child tested. Parents, children (if old enough to understand) and doctors should decide together.

There are some good and bad points to having your child tested. Your doctor can put you in touch with a kidney specialist and a specialist in inherited conditions to help think it through.

Some of the good sides are:

  • Often, the test gives a clear answer on whether or not a child has ADPKD. This can mean less uncertainty for you and your child.
  • If your child is diagnosed with ADPKD, you and they can mentally prepare for the future. For example, you can get used to the idea that they may need dialysis or a transplant when they’re older.
  • If your child’s test confirms they don’t have ADPKD, it will be a relief and mean you and they worry less about their future.
  • If new treatments for ADPKD become available, doctors may be able to offer these to your child.

Some of the downsides are:

  • Sometimes, a test for ADPKD doesn’t give a clear answer on whether or not a child has ADPKD. This can be frustrating.
  • Some children might regret knowing that they have ADPKD because it makes them worry or feel different to others.
  • If your child is diagnosed with ADPKD, doctors won’t be able to tell you with certainty how it will affect them and at what age.
  • If your child is diagnosed with ADPKD, this could affect their health insurance or life insurance.

To help you talk about ADPKD as a family, see our web page Talking to children and young people. We also have a web page on insurance.

If you decide not to get your child tested for ADPKD yet, it’s still a good idea to have their blood pressure checked every year or so.

Check-ups for children with ADPKD

Children with ADPKD are unlikely to show symptoms, although changes are already starting in their kidneys. This is where check-ups can help.

The aims of check-ups for children with ADPKD are:

  • to check for high blood pressure
  • to check for signs of kidney damage
  • to give advice and support

Children with ADPKD usually have a check-up once every year or two. This includes a blood pressure test. Your child’s kidney specialist (nephrologist) might suggest other tests too, depending on your child’s symptoms and kidney health.

Your child will continue to have check-ups as an adult.

Blood pressure checks

About 1 in every 5 children with ADPKD has high blood pressure (hypertension). It’s more common in children with a parent whose ADPKD progressed quickly.

High blood pressure becomes more likely as people get older and their ADPKD gets worse.

Having high blood pressure might put strain on the heart and blood vessels.Because of this, experts recommend that all children diagnosed with ADPKD (or at risk of having ADPKD) have a blood pressure check done at the doctor’s every 1 or 2 years.Children with high blood pressure can take medicines to reduce it.

A blood pressure check is quick and simple. It involves your child wearing a blood pressure cuff on their arm for a minute or so while it measures the pressure of their blood.

A picture showing a person having a blood pressure reading. They have a cuff wrapped around their upper arm. Their lower arm is resting on a table. A cable comes from the cuff to a device which displays their blood pressure.

If your child is aged 5 years or older, your doctor might recommend they have a blood pressure check using a device that measures their blood pressure at home over 24 hours. This is called ‘24-hour blood pressure monitoring’ or ‘ambulatory blood pressure monitoring’. The cuff inflates and deflates automatically many times over 24 hours, both day and night.

If 24-hour blood pressure monitoring is not available or suitable for your child, it’s okay to have a blood pressure check at the doctor’s or using a home monitor instead.

Some parents and children find it reassuring to do regular blood pressure checks at home. If you decide to buy a blood pressure monitor, make sure you use a cuff the right size for your child’s arm. This helps you get accurate readings.

If your child could have ADPKD but you have chosen not to get them tested for yet, they can still have blood pressure checks.

If your child is diagnosed with high blood pressure, your doctor might refer them to a heart specialist (cardiologist) to check their heart. This test is called an echocardiogram and uses ultrasound to make an image of the heart. The cardiologist can use an echocardiogram to check your child doesn’t have a thickened heart wall (called left ventricular hypertrophy). This can sometimes happen as a result of high blood pressure.

Urine tests

Urine tests show how well your child’s kidneys are working. If their kidneys are not working as well as they should, protein levels in their pee will rise. Experts are not sure how often it’s best to do urine tests in children with ADPKD. Your doctor is likely to suggest a test every few years, depending on your child’s kidney health.

Kidney scans

Doctors can use scans, such as an ultrasound scan or magnetic resonance imaging (MRI), to check the size of your child’s kidneys and to look for cysts. This helps your doctor to work out how quickly your child’s ADPKD is getting worse.

How often your child has a scan will depend, in part, on whether they have symptoms:

  • If your child’s ADPKD is getting worse, they may have scans up to once a year.
  • If your child has no symptoms or cysts, they might not need another scan until they’re 15 to 18 years old.

Why scans for brain aneurysms aren’t routine

A brain aneurysm is a swollen blood vessel, like a small berry, in the brain. They can occur in adults with ADPKD. Uncommonly they can burst, which is dangerous.

However, it’s rare for children with ADPKD to get a brain aneurysm, and it’s extremely rare for them to burst in children.

Hundreds of thousands of children across the world have ADPKD, yet there are very few reports of brain aneurysms causing problems in children.

Because of the low risk, experts recommend that children should not routinely have brain scans to check for aneurysms. The risks that come with these scans and with treatment (if needed) could be greater than the benefits.

We understand that brain aneurysms can be a scary thought for parents and children. If they’re causing you or your child ongoing worry, talk to your child’s GP or kidney specialist.

Do children with ADPKD need treatment?

Most children with ADPKD don’t need treatment for ADPKD or its symptoms until they reach adulthood.

A person holding a packet of tablets.

Treating high blood pressure

If your child has high blood pressure, your doctor might refer them to a specialist in childhood kidney conditions (a paediatric nephrologist) or other local expert.

The doctor or specialist may recommend a medicine such as an ACE inhibitor (angiotensin-converting enzyme inhibitor) or ARB (angiotensin receptor blocker) to reduce your child’s blood pressure. This is to help protect your child’s kidneys and reduce their risk of having heart problems or blood vessel disease in the future.

Ask your doctor to explain the benefits and risks of different medicines available for your child.

Treating a urinary tract infection

If your child has a urinary tract infection, their doctor will treat this with antibiotics.

Treating tummy pain

If your child has abdominal (tummy) pain, it’s unlikely to be caused by their ADPKD. To be sure, their doctor might want to do tests to check for an infected or bleeding cyst or a kidney stone. This will depend on your child’s symptoms.

Doctors usually recommend that children with ADPKD don’t take non-steroidal anti-inflammatory drugs (for example ibuprofen or Nurofen®). These medicines can harm the kidneys of people with ADPKD.

Your doctor or pharmacist can recommend safer painkillers for your child.

Medicines to slow ADPKD progression

Currently, there are no medicines to stop ADPKD worsening in children.

A drug called tolvaptan (brand name Jinarc®) can help to slow down kidney damage in some adults but it’s not licensed for use in children.

A recent trial found some evidence that tolvaptan might work in children. Children taking tolvaptan had less growth in their kidney size than children taking a placebo (‘dummy’ pill). Side effects that could affect a child’s day-to-day life were common, such as thirst and weeing often.

The trial was short and the results were not strong enough to pass statistical tests. More research is needed before experts can decide whether tolvaptan is suitable for children.

Helping children with ADPKD to stay healthy

Parents often ask us if there is anything they can do to protect their child’s kidneys from damage. Unfortunately, doctors have few answers. A healthy diet and lifestyle are good for all children, whether or not they have ADPKD. Here is a summary of what we know so far:

Diet and lifestyle

No specific diets have been tested in children with ADPKD. A normal healthy diet is thought to be fine. Children with ADPKD should eat a normal amount of protein, not an unusually high amount.

Weight

ADPKD might start to cause changes to the kidneys sooner in people who are overweight or obese. A healthy diet and exercise can help your child to stay a healthy weight.

Salt

Eating too much salt can speed up kidney damage in adults with ADPKD. Although we don’t know whether salt affects children in the same way, it’s a good idea to help your child avoid too much salt.

The NHS has general advice on how much salt children should eat according to their age. Don’t add salt to your child’s food. Avoid processed foods as much as possible, as these tend to have a lot of salt.

Drinking fluid

It’s not proven that drinking extra fluid can help children with ADPKD. Your child should drink enough to avoid feeling thirsty, but they don’t need to drink unusually large amounts. You can check that your child is drinking enough by looking at the colour of their urine — it should be clear to light yellow.

Dangerous sports

If your child has very large kidneys or cysts that tend to bleed, their kidney specialist may recommend that they avoid some sports (for example, rugby or martial arts). This is to reduce the risk of them injuring their kidneys. This doesn’t mean your child needs to avoid all sport.

Smoking

Explain to your child the dangers of smoking. As well as the usual risks (including cancer), smoking can increase the speed at which ADPKD worsens and can lead to kidney damage.

Medicines to avoid

Always check with your doctor or pharmacist before giving your child any medicine to check it’s safe for them. This includes medicines you can buy without a prescription. Most medicines are fine but some can damage the kidneys of people with a kidney condition.

Examples of medicines that people with a kidney condition should only take if a doctor says it’s okay are non-steroidal anti-inflammatory drugs (ibuprofen and Nurofen®).

Ask for safe alternatives for your child.

More from the PKD Charity

Information and support from others

Further information

All of our publications are based on references but these are removed for ease of reading on our webpages. A version of this webpage with references included is available upon request by emailing [email protected]

Authors and contributors

Written by Dr Matko Marlais, Consultant Nephrologist, Great Ormond Street Hospital, London, and Hannah Bridges PhD, Medical Writer, HB Health Comms Ltd, London.

With thanks to all those the people affected by ADPKD who contributed to this publication.

Last updated: © February 2025 (v3.0).

Due for medical review: February 2028.

Ref No: ADPKD.ICYP.V3.0

Disclaimer: This information is primarily for people in the UK. We have made every effort to ensure that the information we provide is correct and up to date. However, it is not a substitute for professional medical advice or a medical examination. We do not promote or recommend any treatment. We do not accept liability for any errors or omissions. Medical information, the law and government regulations change rapidly, so always consult your GP, pharmacist or other medical professional if you have any concerns or before starting any new treatment.

If you don't have access to a printer and would like a printed version of this information sheet, or any other PKD Charity information, call the PKD Charity Helpline on 0300 111 1234 (weekdays, 9am–5pm) or email [email protected]

The PKD Charity Helpline offers confidential support and information to anyone affected by PKD, including family, friends, carers, newly diagnosed or those who have lived with the condition for many years.
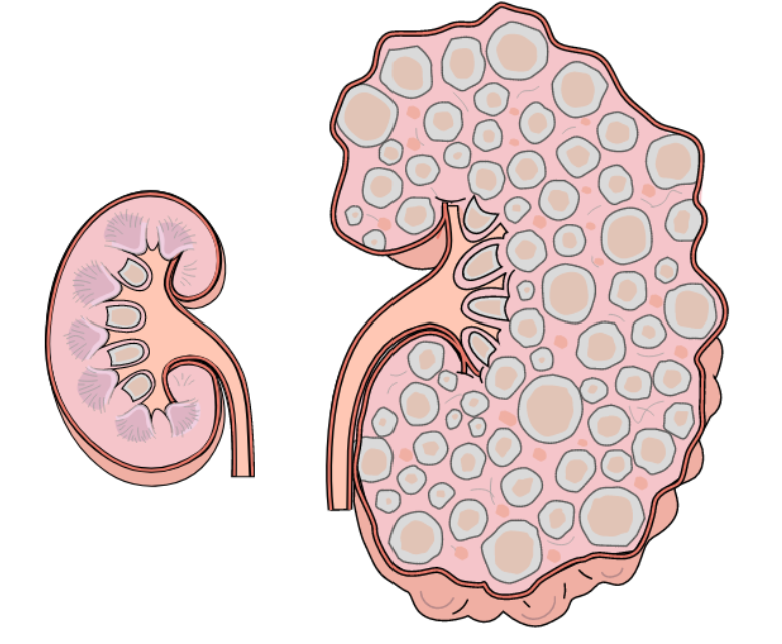
Read more …Symptoms and testing in children

Feedback

We welcome feedback on the information provided on this webpage. If you have any feedback regarding the information provided on this webpage, please complete the Feedback Form